

Heightmaxxing with Erdafinitib - summary of a study.

Fuldblod

Fuldblod

wonderfully mysterious
Joined
Mar 8, 2026
Posts
1,150
Reputation
1,118
Paper: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1

Will make this short, nothing fancy
Still rep because this is the greatest hopefuel you'll ever read.

These researchers have studied a causal relationship between the use of igf-1 and erdafinitibs inhibitory effects.
See this excerpt
Erdafinitib inhibits PI3K/AKT and MAPK/ERK signaling pathways.
During erdafinitib inhibition, IGF-1 can activate the PI3K/AKT pathway but not the MAPK/ERK pathway.

The researchers speculate this might be the cause for profound longitudinal growth seen in case studies of extreme growth spurts in cancer kids using erdafinitib.
This clearly suggests that the inhibition of MAPK/ERK and promotion of PI3K/AKT simultaneously causes rapid height gain / growth

Take a look at these figures.
Patient 1 started GH at 8yr to treat GHD (Growth hormone deficiency) And is treated with erdafinitib to treat a brain tumor. (mesencephalic glioma)
1784459209239

So basically kid no. 1 only gets thick bones in his hand as a result.
pretty cheap for good height gains. (still sub 180 tho:ROFLMAO::ROFLMAO:)

Another one:
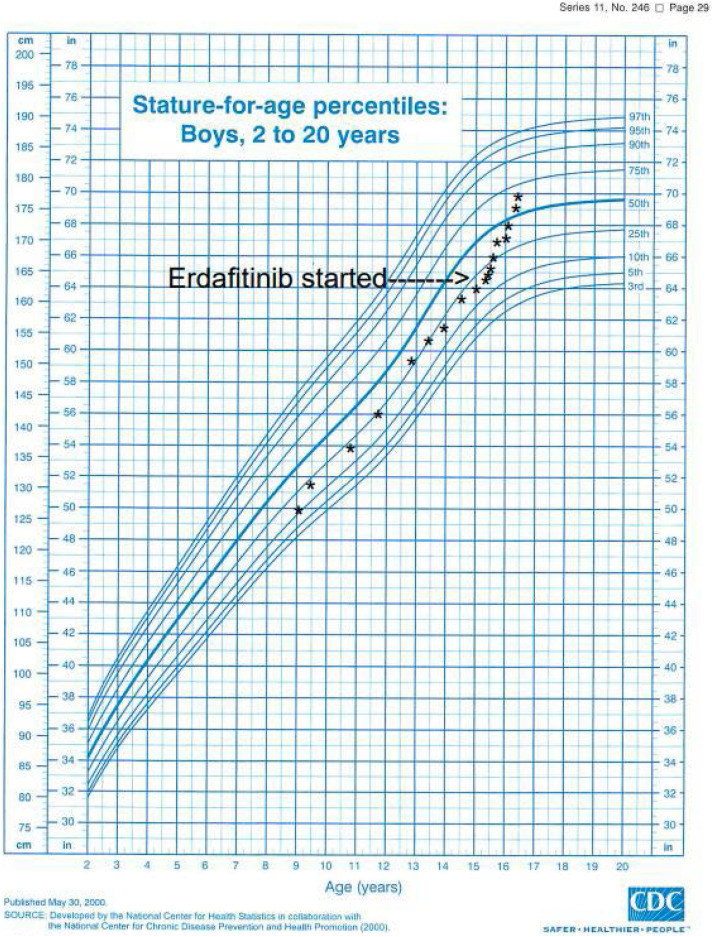
Patient started 7mg/day erdafinitib at 15 yr and 4 months, Experienced many treatment pauses because of hyperphosphatemia and was using high doses of phosphate binding medicine to combat this.
5 months after treatment with erdafinitib starts, the dose is lowered to 5mg/day due to relocation and to lower treatment pauses.
Patient was on erdafinitib to treat cancer and has an "activating FGFR1 variant" (gene mutation that causes overexpression of FGFR1 gene)
1 s20 S2405844024069184 gr1

Kid goes from 10 cm/yr AGV, to 19 cm/yr AGV. Pretty insane.
However the consequences are concerning.


1 s20 S2405844024069184 gr2 lrg

Fig. 2. Abnormal rapid skeletal growth in a patient treated with erdafitinib, a pan-FGFR inhibitor.
A. X-ray of the cervical and thoracic spine before treatment (a, b, and c) and 9 months after treatment (d, e, f, g, h, and i) with erdafitinib showing the development of cervical lordosis and thoracic scoliosis.
B. MRI images (sagittal, T1 post- Contrast Fat saturation (FS) pulse sequences) of the cervical, thoracic, and lumbar spine demonstrating the development and progression of spinal deformities after commencing erdafitinib: a. Baseline; b. at 2 months; c. at 5 months; d. at 9 months; e. at 12 months which was 3 months after cessation of erdafitinib and after cervical deformity surgical correction.

In short: He needed surgery because his spine had crumpled into a C shape around the neck area.
You can see the spinal development if you look from left to right.

Bone analysis revealed that his bone density was equal to that of osteoporosis.
"0.6322 gm/sq.cm, which is −3.8 standard deviation below the mean value for the age-matched population and more than 2.5 standard deviations below the value for males at peak bone mass."
All hormonal markers (hgh, test, IGF-1 ETC..) Stayed within normal range during treatment. i.e. you don't need to blast gh when on ts.

It's pretty clear that erda is a potent and strong drug to increase height velocity. But the sideeffect profile is just as dire. Stick to a low dose and don't use it for longer than 6 months unless you want to look like a camel-necked freak...

I've got no more time saars. read the rest if you want to - it's a really interesting study.
Start from here: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1:~:text=Bone age assessments had not been performed prior to or during erdafitinib therapy. At cessation of therapy, bone
 
Last edited:
  • +1
Reactions: BronzeAlligator1, jeremyy, jjams and 6 others
The first photo (with 2 patients) is from a different paper than the first link given.
This is the link for that one.

After that we follow paper #1

Wrote this shit in a jiffy so i just had to clairfy
 
  • +1
Reactions: bluebandz
Paper: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1

Will make this short, nothing fancy
Still rep because this is the greatest hopefuel you'll ever read.

These researchers have studied a causal relationship between the use of igf-1 and erdafinitibs inhibitory effects.
See this excerpt
Erdafinitib inhibits PI3K/AKT and MAPK/ERK signaling pathways.
During erdafinitib inhibition, IGF-1 can activate the PI3K/AKT pathway but not the MAPK/ERK pathway.

The researchers speculate this might be the cause for profound longitudinal growth seen in case studies of extreme growth spurts in cancer kids using erdafinitib.
This clearly suggests that the inhibition of MAPK/ERK and promotion of PI3K/AKT simultaneously causes rapid height gain / growth

Take a look at these figures.
Patient 1 started GH at 8yr to treat GHD (Growth hormone deficiency) And is treated with erdafinitib to treat a brain tumor. (mesencephalic glioma)
View attachment 5385363
So basically kid no. 1 only gets thick bones in his hand as a result.
pretty cheap for good height gains. (still sub 180 tho:ROFLMAO::ROFLMAO:)

Another one:
Patient started 7mg/day erdafinitib at 15 yr and 4 months, Experienced many treatment pauses because of hyperphosphatemia and was using high doses of phosphate binding medicine to combat this.
5 months after treatment with erdafinitib starts, the dose is lowered to 5mg/day due to relocation and to lower treatment pauses.
Patient was on erdafinitib to treat cancer and has an "activating FGFR1 variant" (gene mutation that causes overexpression of FGFR1 gene)
View attachment 5385366
Kid goes from 10 cm/yr AGV, to 19 cm/yr AGV. Pretty insane.
However the consequences are concerning.


View attachment 5385398
Fig. 2. Abnormal rapid skeletal growth in a patient treated with erdafitinib, a pan-FGFR inhibitor.
A. X-ray of the cervical and thoracic spine before treatment (a, b, and c) and 9 months after treatment (d, e, f, g, h, and i) with erdafitinib showing the development of cervical lordosis and thoracic scoliosis.
B. MRI images (sagittal, T1 post- Contrast Fat saturation (FS) pulse sequences) of the cervical, thoracic, and lumbar spine demonstrating the development and progression of spinal deformities after commencing erdafitinib: a. Baseline; b. at 2 months; c. at 5 months; d. at 9 months; e. at 12 months which was 3 months after cessation of erdafitinib and after cervical deformity surgical correction.

In short: He needed surgery because his spine had crumpled into a C shape around the neck area.
You can see the spinal development if you look from left to right.

Bone analysis revealed that his bone density was equal to that of osteoporosis.
"0.6322 gm/sq.cm, which is −3.8 standard deviation below the mean value for the age-matched population and more than 2.5 standard deviations below the value for males at peak bone mass."
All hormonal markers (hgh, test, IGF-1 ETC..) Stayed within normal range during treatment. i.e. you don't need to blast gh when on ts.

It's pretty clear that erda is a potent and strong drug to increase height velocity. But the sideeffect profile is just as dire. Stick to a low dose and don't use it for longer than 6 months unless you want to look like a camel-necked freak...

I've got no more time saars. read the rest if you want to - it's a really interesting study.
Start from here: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1:~:text=Bone age assessments had not been performed prior to or during erdafitinib therapy. At cessation of therapy, bone
i feel like erda is pretty overrated, the sides are often not worth it
 
  • +1
Reactions: mendeds, idontmogYET, Ahmed88 and 4 others
Forgot to mention that the synergy between igf-1 and erdafinitib is to be used carefully - as shown in these 3 cases, both patients who experienced rapid height growth also got skeletal deformations. Food for thought.

Although for oldcells 16-21 with a low AGV it should not be of much concern
 
i feel like erda is pretty overrated, the sides are often not worth it
Actually it’s not that bad.
Some changes were reversible as seen in the x-rays of the 1. Photo.
And if you stick to a low dose (3mg) and don’t exceed 6months of treatment.
I believe the side effect profile on skeletal development shouldn’t be too bad.
Keep in mind that both patients were in their peak of natural growth velocity.
rapid skeletal advancements wouldn’t happen for a guy like me (19yrs) but still growing
 
Last edited:
  • +1
Reactions: nwed
Paper: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1

Will make this short, nothing fancy
Still rep because this is the greatest hopefuel you'll ever read.

These researchers have studied a causal relationship between the use of igf-1 and erdafinitibs inhibitory effects.
See this excerpt
Erdafinitib inhibits PI3K/AKT and MAPK/ERK signaling pathways.
During erdafinitib inhibition, IGF-1 can activate the PI3K/AKT pathway but not the MAPK/ERK pathway.

The researchers speculate this might be the cause for profound longitudinal growth seen in case studies of extreme growth spurts in cancer kids using erdafinitib.
This clearly suggests that the inhibition of MAPK/ERK and promotion of PI3K/AKT simultaneously causes rapid height gain / growth

Take a look at these figures.
Patient 1 started GH at 8yr to treat GHD (Growth hormone deficiency) And is treated with erdafinitib to treat a brain tumor. (mesencephalic glioma)
View attachment 5385363
So basically kid no. 1 only gets thick bones in his hand as a result.
pretty cheap for good height gains. (still sub 180 tho:ROFLMAO::ROFLMAO:)

Another one:
Patient started 7mg/day erdafinitib at 15 yr and 4 months, Experienced many treatment pauses because of hyperphosphatemia and was using high doses of phosphate binding medicine to combat this.
5 months after treatment with erdafinitib starts, the dose is lowered to 5mg/day due to relocation and to lower treatment pauses.
Patient was on erdafinitib to treat cancer and has an "activating FGFR1 variant" (gene mutation that causes overexpression of FGFR1 gene)
View attachment 5385366
Kid goes from 10 cm/yr AGV, to 19 cm/yr AGV. Pretty insane.
However the consequences are concerning.


View attachment 5385398
Fig. 2. Abnormal rapid skeletal growth in a patient treated with erdafitinib, a pan-FGFR inhibitor.
A. X-ray of the cervical and thoracic spine before treatment (a, b, and c) and 9 months after treatment (d, e, f, g, h, and i) with erdafitinib showing the development of cervical lordosis and thoracic scoliosis.
B. MRI images (sagittal, T1 post- Contrast Fat saturation (FS) pulse sequences) of the cervical, thoracic, and lumbar spine demonstrating the development and progression of spinal deformities after commencing erdafitinib: a. Baseline; b. at 2 months; c. at 5 months; d. at 9 months; e. at 12 months which was 3 months after cessation of erdafitinib and after cervical deformity surgical correction.

In short: He needed surgery because his spine had crumpled into a C shape around the neck area.
You can see the spinal development if you look from left to right.

Bone analysis revealed that his bone density was equal to that of osteoporosis.
"0.6322 gm/sq.cm, which is −3.8 standard deviation below the mean value for the age-matched population and more than 2.5 standard deviations below the value for males at peak bone mass."
All hormonal markers (hgh, test, IGF-1 ETC..) Stayed within normal range during treatment. i.e. you don't need to blast gh when on ts.

It's pretty clear that erda is a potent and strong drug to increase height velocity. But the sideeffect profile is just as dire. Stick to a low dose and don't use it for longer than 6 months unless you want to look like a camel-necked freak...

I've got no more time saars. read the rest if you want to - it's a really interesting study.
Start from here: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1:~:text=Bone age assessments had not been performed prior to or during erdafitinib therapy. At cessation of therapy, bone
So,basically height maxxing with alot of chances of good results
 
  • +1
Reactions: Fuldblod
So,basically height maxxing with alot of chances of good results
the theory checks out so well.
It really should work like miracles.
But who knows what reality will show.
I’m getting some xrays soon.
If they’re open im hopping on twinnem.
Low dose 6months
 
  • +1
Reactions: Nikmaxxer
i feel like erda is pretty overrated, the sides are often not worth it
“the most common toxicities associated with erdafitinib and other FGFR inhibitors include hyperphosphatemia, skin, and nail toxicities, as well as hand and foot syndrome (redness, swelling, peeling, or tenderness on the hands or feet) [10].”

“A novel mutation in FGFR3 causes camptodactyly, tall stature, and hearing loss (CATSHL) syndrome. Am J Hum Genet. 2006;79(5):935–41.”

Side effect profile seems quite mild as the eye and hearing problems are rarely reported in use with erdafinitib.
Skeletal disfiguration/deformities can be mitigated by not taking the shit at your peak AGV age.
 
  • +1
Reactions: nwed
Doesnt prove anything related to an improved mechanism when combining Erda and GH
 
  • +1
Reactions: Fuldblod
Doesnt prove anything related to an improved mechanism when combining Erda and GH
ofcourse not.
It’s about erda and igf-1
I don’t know about any gh with this, but the connection between erda and igf-1 the researchers found is genuine
 
  • +1
  • JFL
Reactions: fraudster#1 and Niebvll
Do you know what HGH gets converted to in the liver

:feelsuhh:
Ok so well then it means hgh and erda works synergystically downstream.
I don’t get your point here?
 
Ok so well then it means hgh and erda works synergystically downstream.
I don’t get your point here?
My point is that it does not mean that
1. They literally bathed the cells in vitro in igf1, you couldnt recreate this exposure with just injecting GH
2. n=1, are we deadass?
3. Its not synergystically at all, the IGF1 actually goes against the effects of Erdafitinib that would lead to apoptosis
Its a cool thought and shouldnt be overlooked but saying that this is definitive evidence for anything is highly exaggerated
 
  • +1
Reactions: Fuldblod
My point is that it does not mean that
1. They literally bathed the cells in vitro in igf1, you couldnt recreate this exposure with just injecting GH
2. n=1, are we deadass?
3. Its not synergystically at all, the IGF1 actually goes against the effects of Erdafitinib that would lead to apoptosis
Its a cool thought and shouldnt be overlooked but saying that this is definitive evidence for anything is highly exaggerated
Du bist so klug lieber mann
 
  • +1
Reactions: Niebvll
Bist du deutsch?
ne
Ich bin dänisch aber mein deutsch lehrerin geb mir 10 (1 von die beste) in deutsch🥺🥺🥺
Doch mein grammatik ist scheisse..
 
  • +1
Reactions: Niebvll
ne
Ich bin dänisch aber mein deutsch lehrerin geb mir 10 (1 von die beste) in deutsch🥺🥺🥺
Doch mein grammatik ist scheisse..
Ok krass
Wohnst du nah an der Grenze
Komme aus Kiel:Comfi:
 
  • +1
Reactions: Fuldblod
Ok krass
Wohnst du nah an der Grenze
Komme aus Kiel:Comfi:
😂nein, bin aus midtjylland horsens.
Ich fahre nach Tarp später so ich kann mit interrail um Europa fahren.
 
  • +1
Reactions: Niebvll
My point is that it does not mean that
1. They literally bathed the cells in vitro in igf1, you couldnt recreate this exposure with just injecting GH
2. n=1, are we deadass?
3. Its not synergystically at all, the IGF1 actually goes against the effects of Erdafitinib that would lead to apoptosis
Its a cool thought and shouldnt be overlooked but saying that this is definitive evidence for anything is highly exaggerated
man fuck this bullshit i dont jack shit about any of this shit man

You say erdafinitib caused apoptosis.
And that Igf-1 prevents this?
Correct?
Apoptosis in general is just cell death.
Perhaps it’s because it plays a bigger role in the epiphysis? Am i missing some crucial knowledge here?

As far as i know, igf-1 preventing random apoptosis around the body wouldn’t effect the growth axis…
 
man fuck this bullshit i dont jack shit about any of this shit man

You say erdafinitib caused apoptosis.
And that Igf-1 prevents this?
Correct?

Apoptosis in general is just cell death.
Its programmed cell suicide not just random cell death
Perhaps it’s because it plays a bigger role in the epiphysis? Am i missing some crucial knowledge here?

As far as i know, igf-1 preventing random apoptosis around the body wouldn’t effect the growth axis…
Again, not random
Have you even taken a look at your own study? This was clearly talked about there
Erdafitinib kills off the fibroblasts due to inhibiting their survival pathways, thats why igf1 was used as co-treatment
 
  • +1
Reactions: Fuldblod
Erdafitinib kills off the fibroblasts due to inhibiting their survival pathways, thats why igf1 was used as co-treatment
So HGH should be used with Erdafitinib? I don't get it.
 
  • +1
Reactions: Fuldblod and Niebvll
So HGH should be used with Erdafitinib? I don't get it.
You can do that but it wont recreate the exposure in the in vitro study
Probably does have a similar effect though on a higher dosage
 
  • +1
Reactions: Fuldblod and cowmuncher26
So running low dose erda (like 3-4mg) for under 6 months really shouldnt be a problem? Why isn’t everybody on this
 
  • +1
Reactions: Fuldblod
  • +1
Reactions: Fuldblod and fraudster#1
Calling that "low dose" is impressive
Just a normal therapeutic dose

Maybe because its a cancerdrug
Wasnt normal therapeutic doses 8mg?

And also, what does that say? Thats it’s a "cancer drug" What would be so bad about taking it?
 
  • +1
Reactions: Fuldblod
Paper: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1

Will make this short, nothing fancy
Still rep because this is the greatest hopefuel you'll ever read.

These researchers have studied a causal relationship between the use of igf-1 and erdafinitibs inhibitory effects.
See this excerpt
Erdafinitib inhibits PI3K/AKT and MAPK/ERK signaling pathways.
During erdafinitib inhibition, IGF-1 can activate the PI3K/AKT pathway but not the MAPK/ERK pathway.

The researchers speculate this might be the cause for profound longitudinal growth seen in case studies of extreme growth spurts in cancer kids using erdafinitib.
This clearly suggests that the inhibition of MAPK/ERK and promotion of PI3K/AKT simultaneously causes rapid height gain / growth

Take a look at these figures.
Patient 1 started GH at 8yr to treat GHD (Growth hormone deficiency) And is treated with erdafinitib to treat a brain tumor. (mesencephalic glioma)
View attachment 5385363
So basically kid no. 1 only gets thick bones in his hand as a result.
pretty cheap for good height gains. (still sub 180 tho:ROFLMAO::ROFLMAO:)

Another one:
Patient started 7mg/day erdafinitib at 15 yr and 4 months, Experienced many treatment pauses because of hyperphosphatemia and was using high doses of phosphate binding medicine to combat this.
5 months after treatment with erdafinitib starts, the dose is lowered to 5mg/day due to relocation and to lower treatment pauses.
Patient was on erdafinitib to treat cancer and has an "activating FGFR1 variant" (gene mutation that causes overexpression of FGFR1 gene)
View attachment 5385366
Kid goes from 10 cm/yr AGV, to 19 cm/yr AGV. Pretty insane.
However the consequences are concerning.


View attachment 5385398
Fig. 2. Abnormal rapid skeletal growth in a patient treated with erdafitinib, a pan-FGFR inhibitor.
A. X-ray of the cervical and thoracic spine before treatment (a, b, and c) and 9 months after treatment (d, e, f, g, h, and i) with erdafitinib showing the development of cervical lordosis and thoracic scoliosis.
B. MRI images (sagittal, T1 post- Contrast Fat saturation (FS) pulse sequences) of the cervical, thoracic, and lumbar spine demonstrating the development and progression of spinal deformities after commencing erdafitinib: a. Baseline; b. at 2 months; c. at 5 months; d. at 9 months; e. at 12 months which was 3 months after cessation of erdafitinib and after cervical deformity surgical correction.

In short: He needed surgery because his spine had crumpled into a C shape around the neck area.
You can see the spinal development if you look from left to right.

Bone analysis revealed that his bone density was equal to that of osteoporosis.
"0.6322 gm/sq.cm, which is −3.8 standard deviation below the mean value for the age-matched population and more than 2.5 standard deviations below the value for males at peak bone mass."
All hormonal markers (hgh, test, IGF-1 ETC..) Stayed within normal range during treatment. i.e. you don't need to blast gh when on ts.

It's pretty clear that erda is a potent and strong drug to increase height velocity. But the sideeffect profile is just as dire. Stick to a low dose and don't use it for longer than 6 months unless you want to look like a camel-necked freak...

I've got no more time saars. read the rest if you want to - it's a really interesting study.
Start from here: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1:~:text=Bone age assessments had not been performed prior to or during erdafitinib therapy. At cessation of therapy, bone
2-4mg max
 
  • +1
Reactions: Fuldblod
4 to 8


clearly not enough research buddy:trepidation:
Yeah i know i havent really done too much research on it, but thats why I am asking. What could be the worst? Ive seen people talk about blindness but that only happenned to 1 guy om a High dose for a long time. Other than I have only seen stuff like nail damage
 
  • +1
Reactions: Fuldblod
Yeah i know i havent really done too much research on it, but thats why I am asking. What could be the worst?
cba listing it all nigger
Ive seen people talk about blindness but that only happenned to 1 guy om a High dose for a long time. Other than I have only seen stuff like nail damage
DNR
 
  • +1
Reactions: Fuldblod
First of all: This is a very weak study

Second of of all: These kids have CNS tumors, prior brain surgery/radiation/chemotherapy, major hypothalamic pituitary disruption, GH deficiency, very very little sex hormones, probably high fgfr3 and impaired puberty signaling

Third of all: None of these kids showed any signs of infrease in final adult height, only increased catch up growth, even with all that
 
  • Ugh..
  • +1
Reactions: Fuldblod and Niebvll
First of all: This is a very weak study

Second of of all: These kids have CNS tumors, prior brain surgery/radiation/chemotherapy, major hypothalamic pituitary disruption, GH deficiency, very very little sex hormones, probably high fgfr3 and impaired puberty signaling

Third of all: None of these kids showed any signs of infrease in final adult height, only increased catch up growth, even with all that
clearly not.
You can see how their growth trajectory changes completely.
Leaps and bounds.
It’s literally putting them in a different percentile.
How is going from 150 FAH to 175 FAH not an increase?
 
the theory checks out so well.
It really should work like miracles.
But who knows what reality will show.
I’m getting some xrays soon.
If they’re open im hopping on twinnem.
Low dose 6months
ill be your test subject if you tell me how much to take and what to take to stop side effects :lul:
 
  • +1
Reactions: Fuldblod
Paper: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1

Will make this short, nothing fancy
Still rep because this is the greatest hopefuel you'll ever read.

These researchers have studied a causal relationship between the use of igf-1 and erdafinitibs inhibitory effects.
See this excerpt
Erdafinitib inhibits PI3K/AKT and MAPK/ERK signaling pathways.
During erdafinitib inhibition, IGF-1 can activate the PI3K/AKT pathway but not the MAPK/ERK pathway.

The researchers speculate this might be the cause for profound longitudinal growth seen in case studies of extreme growth spurts in cancer kids using erdafinitib.
This clearly suggests that the inhibition of MAPK/ERK and promotion of PI3K/AKT simultaneously causes rapid height gain / growth

Take a look at these figures.
Patient 1 started GH at 8yr to treat GHD (Growth hormone deficiency) And is treated with erdafinitib to treat a brain tumor. (mesencephalic glioma)
View attachment 5385363
So basically kid no. 1 only gets thick bones in his hand as a result.
pretty cheap for good height gains. (still sub 180 tho:ROFLMAO::ROFLMAO:)

Another one:
Patient started 7mg/day erdafinitib at 15 yr and 4 months, Experienced many treatment pauses because of hyperphosphatemia and was using high doses of phosphate binding medicine to combat this.
5 months after treatment with erdafinitib starts, the dose is lowered to 5mg/day due to relocation and to lower treatment pauses.
Patient was on erdafinitib to treat cancer and has an "activating FGFR1 variant" (gene mutation that causes overexpression of FGFR1 gene)
View attachment 5385366
Kid goes from 10 cm/yr AGV, to 19 cm/yr AGV. Pretty insane.
However the consequences are concerning.


View attachment 5385398
Fig. 2. Abnormal rapid skeletal growth in a patient treated with erdafitinib, a pan-FGFR inhibitor.
A. X-ray of the cervical and thoracic spine before treatment (a, b, and c) and 9 months after treatment (d, e, f, g, h, and i) with erdafitinib showing the development of cervical lordosis and thoracic scoliosis.
B. MRI images (sagittal, T1 post- Contrast Fat saturation (FS) pulse sequences) of the cervical, thoracic, and lumbar spine demonstrating the development and progression of spinal deformities after commencing erdafitinib: a. Baseline; b. at 2 months; c. at 5 months; d. at 9 months; e. at 12 months which was 3 months after cessation of erdafitinib and after cervical deformity surgical correction.

In short: He needed surgery because his spine had crumpled into a C shape around the neck area.
You can see the spinal development if you look from left to right.

Bone analysis revealed that his bone density was equal to that of osteoporosis.
"0.6322 gm/sq.cm, which is −3.8 standard deviation below the mean value for the age-matched population and more than 2.5 standard deviations below the value for males at peak bone mass."
All hormonal markers (hgh, test, IGF-1 ETC..) Stayed within normal range during treatment. i.e. you don't need to blast gh when on ts.

It's pretty clear that erda is a potent and strong drug to increase height velocity. But the sideeffect profile is just as dire. Stick to a low dose and don't use it for longer than 6 months unless you want to look like a camel-necked freak...

I've got no more time saars. read the rest if you want to - it's a really interesting study.
Start from here: https://www.sciencedirect.com/science/article/pii/S2405844024069184#fig1:~:text=Bone age assessments had not been performed prior to or during erdafitinib therapy. At cessation of therapy, bone
heavy mirin bro great thread i do for sure feel bad for those who are struggling with cancer though
Mirin
 
  • +1
Reactions: Fuldblod
ill be your test subject if you tell me how much to take and what to take to stop side effects :lul:
heavy mirin bro great thread i do for sure feel bad for those who are struggling with cancer though
Mirin
Erda has a very high risk profile.
I’ll start 0.5mg/kg/ed infig instead.
Also actually being used to make short people taller.
Also doesn’t have the chance to make you blind lol (n=~30)
 
  • +1
Reactions: bluebandz
Erda has a very high risk profile.
I’ll start 0.5mg/kg/ed infig instead.
Also actually being used to make short people taller.
Also doesn’t have the chance to make you blind lol (n=~30)
#gettingnoresults
 
  • Ugh..
  • +1
Reactions: Fuldblod and Ahmed88
clearly not.
You can see how their growth trajectory changes completely.
Leaps and bounds.
It’s literally putting them in a different percentile.
How is going from 150 FAH to 175 FAH not an increase?
A fucking change in PAH during treatment is not evidence of any real increase in genetically determined adult stature, you dense apebrained retard.

Pah algorithms are just mathematical estimates pulled out of their fucking ass from bone age, chronological age, height SDS, pubertal stage, and recent height velocity.

The baseline PAH for those poor niggers was only an estimate of how tall these diseaseridden, sick children were expected to become WITH all their 100 fucking diseases, not how tall a healthy normal child would have become.


When growth dynamics get violently the predicted number can jump all over the place with zero guarantee that final adult height will actually increase for shit, doesnt take a genius to figure that out, now does it?

Also you’re completely ignoring the fact that these kids aren’t even close to fucking normal, you fucking retarded cunt.
 
  • Ugh..
  • +1
Reactions: Fuldblod and Niebvll
A fucking change in PAH during treatment is not evidence of any real increase in genetically determined adult stature, you dense apebrained retard.

Pah algorithms are just mathematical estimates pulled out of their fucking ass from bone age, chronological age, height SDS, pubertal stage, and recent height velocity.

The baseline PAH for those poor niggers was only an estimate of how tall these diseaseridden, sick children were expected to become WITH all their 100 fucking diseases, not how tall a healthy normal child would have become.


When growth dynamics get violently the predicted number can jump all over the place with zero guarantee that final adult height will actually increase for shit, doesnt take a genius to figure that out, now does it?

Also you’re completely ignoring the fact that these kids aren’t even close to fucking normal, you fucking retarded cunt.
DNR
Eugh reacted me saying he wont get results
Get your position straight
Youre also completely misinformed as shown by your other post
Theres cohorts with completely normal fgfr3 expression in total and at the growth plates that also show these results
Proving its not about saar fgfr3 mutations
 
  • Ugh..
  • +1
Reactions: Fuldblod and Ahmed88
DNR
Eugh reacted me saying he wont get results
Get your position straight
Youre also completely misinformed as shown by your other post
Theres cohorts with completely normal fgfr3 expression in total and at the growth plates that also show these results
Proving its not about saar fgfr3 mutations
Just did it back, dipshit

Also, it's customary to leave the study link when talking out your ass
 
  • +1
Reactions: Fuldblod
Just did it back, dipshit
Dont do it again boyo or Ill get real mad
Also, it's customary to leave the study link when talking out your ass
As if youd need study links on that
Theres so few trials on it
Can only be thor or nci atp:lul:

My claim of those cohorts existing is also completely logical considering erda is used for fgfr2 mutations as well and patients that only have affected fgfr3 expression in the cancer cells themselves
 
  • +1
Reactions: Fuldblod
Dont do it again boyo or Ill get real mad

As if youd need study links on that
Theres so few trials on it
Can only be thor or nci atp:lul:
Are you fucking dense, nigger?

I asked for the study link, not "muh THOR and NCI and shieet."
My claim of those cohorts existing is also completely logical considering erda is used for fgfr2 mutations as well and patients that only have affected fgfr3 expression in the cancer cells themselves

Oh my fucking god


“Completely logical” isn’t a fucking source. 😂


If you’re making a positive scientific claim, the burden of proof is ON YOU.

You don’t just get to say “muh saar it’s logical” and expect everyone else to accept the random shit you just spewed out of your ass.


Tumor genotype≠nirmal growth plate,
physiology


So stop handwaving like a retard and cite the evidence. If those cohorts exist, it should take you about 30 seconds MAX to link them.
 
  • WTF
  • +1
Reactions: Fuldblod and Niebvll
Are you fucking dense, nigger?

I asked for the study link, not "muh THOR and NCI and shieet."
And I fucking told you I cba getting links for your fuckass

Oh my fucking god

“Completely logical” isn’t a fucking source. 😂

If you’re making a positive scientific claim, the burden of proof is ON YOU.
Did I say it isnt
This isnt even a debate of any sorts
No burden of proof exists
You don’t just get to say “muh saar it’s logical” and expect everyone else to accept the random shit you just spewed out of your ass.

Tumor genotype≠nirmal growth plate,
physiology
???
Thats not what I said?
I said that the patients that did have tumors, had normal growth plate physiology/fgfr3 expression and development because the alterations are cancer cell restricted

So stop handwaving like a retard and cite the evidence. If those cohorts exist, it should take you about 30 seconds MAX to link them.
Again never claimed that as evidence, i noted how its just logical and youre being retarded by not thinking of this
You dont ask for citations when someone talks about GHD cohorts existing in GH treatment trials do you
Same shit

Just for you
CNS tumor patients, normal growth plates, no fgfr3 involvement because the issue was fgfr1 alteration
Still showed a widened growth plate
Theres also feasibility reports on this study so dont say muh methodically bad

Theres a paywalled one that also had such cohorts (https://onlinelibrary.wiley.com/doi/full/10.1002/1545-5017.70046) :feelspepo:

Youre right that thor didnt have no-fgfr3 alteration patients but ragnar did, unfortunately they didnt disclose it for each patient. So the increase in growth could be from fgfr3 alteration patients. NCI did have a case of a 15 year old with wild type fgfr3 (fgfr1 alteration only) and it increased his velocity to 19cm annually
Looking at his trajectory he absolutely smashed the height he wouldve most likely ended up with without treatment, it also seems to me that some sort of catch up growth already atleast partially happened since he went from bottom 10 up to above 25 pct
Other serum markers for growth were noted to be completely normal too
I fucked up the links before but now theyre correct


I dont want to argue about this
You can believe it doesnt work, I believe it does, also to an extent for people with normal fgfr3 expression
 
Last edited:
  • +1
Reactions: Fuldblod
And I fucking told you I cba getting links for your fuckass
Because, no such studies exist... 😂
Did I say it isnt
This isnt even a debate of any sorts
No burden of proof exists
???????????

Yes, there fucking is?

The moment you make a positive factual claim like “saar trust me there are cohorts showing this in patients with normal FGFR3 expression saar" the burden of supporting that claim is on you. That’s how scientific discussion works.


You don’t get to make a claim refuse to provide evidence and then act like everyone else has to accept it because you think it’s “logical.”

If the evidence exists, then cite it nigga. If it doesn’t, then it’s just your inference not an established fact.


???
Thats not what I said?
I said that the patients that did have tumors, had normal growth plate physiology/fgfr3 expression and development because the alterations are cancer cell restricted
That’s still an assumption tho not evidence.


The tumor mutation being cancer cel restricted does not mean the patient’s growth plate physiology was normal.

No FGFR3 mutation ≠ normal skeletal physiology.


Again never claimed that as evidence, i noted how its just logical and youre being retarded by not thinking of this
You dont ask for citations when someone talks about GHD cohorts existing in GH treatment trials do you
Same shit

Just for you
https://doi.org/10.1159/000540485 CNS tumor patients, normal growth plates, no fgfr3 involvement because the issue was fgfr1 alteration
Still showed a widened growth plate
Theres also feasibility reports on this study so dont say muh methodically bad

Theres a paywalled one that also had such cohorts (https://onlinelibrary.wiley.com/doi/full/10.1002/1545-5017.70046) :feelspepo:

Youre right that thor didnt have no-fgfr3 alteration patients but ragnar did, unfortunately they didnt disclose it for each patient. So the increase in growth could be from fgfr3 alteration patients. NCI did have a case of a 15 year old with wild type fgfr3 (fgfr1 alteration only) and it increased his velocity to 19cm annually
Looking at his trajectory he absolutely smashed the height he wouldve most likely ended up with without treatment, it also seems to me that some sort of catch up growth already atleast partially happened since he went from bottom 10 up to above 25 pct
Other serum markers for growth were noted to be completely normal too
Redirecting I fucked up the links before but now theyre correct


I dont want to argue about this
You can believe it doesnt work, I believe it does, also to an extent for people with normal fgfr3 expression
Finally, i see some fucking links for once

Anddddd it's fucking bullshit

First of all, this isn't even evidence for the claim you fucking claimed, it reports increase in GROWTH VELOCITY GROWTHH VELOCITYY not genetically determined final adult height!!!

Accelerated growth during treatment and catch up growth are bery well recognized phenomena and cant be interpreted as evidence of increased adult height without longitudinal endpoint data.


Second of all: you're just removing one sickness and adding another...

fgfr1 or fgfr1 it doesn't change the fact that, they were heavily pretreated pediatric CNS tumor patients with alotttttr of damn problems (i explained this in this thread somewhere).

Yeah this one:
These kids have CNS tumors, prior brain surgery/radiation/chemotherapy, major hypothalamic pituitary disruption, GH deficiency, very very little sex hormones, probably high fgfr3 and impaired puberty signaling

And before you say, "but saar saar cancer cell and shieett bro ong."

Your OWN FUCKING vienna paper (the only fucking paper that actually works), says the following shit not once, not twice but THREE FUCKING TIMES (atleast that's how many i could find):

1:
Linear growth acceleration was independent of sex steroids and IGF1 levels, which is especially remarkable in the context of heavily pretreated pediatric neuro-oncology patients with severe growth impairment before initiation of therapy.

2:
Linear growth acceleration was independent of sex steroids and IGF1 levels, which is especially remarkable in the context of heavily pretreated pediatric neuro-oncology patients with severe growth impairment before initiation of therapy.
3:
The context of heavily pretreated pediatric cancer patients with severe growth impairment before initiation of erdafitinib underlines the hypothetical potential
There's probably more

I could have flamed your ass more, but i just woke up and i need to take shower and get ready.
 
  • +1
Reactions: Niebvll and Fuldblod
Because, no such studies exist... 😂

???????????

Yes, there fucking is?

The moment you make a positive factual claim like “saar trust me there are cohorts showing this in patients with normal FGFR3 expression saar" the burden of supporting that claim is on you. That’s how scientific discussion works.


You don’t get to make a claim refuse to provide evidence and then act like everyone else has to accept it because you think it’s “logical.”

If the evidence exists, then cite it nigga. If it doesn’t, then it’s just your inference not an established fact.


That’s still an assumption tho not evidence.


The tumor mutation being cancer cel restricted does not mean the patient’s growth plate physiology was normal.

No FGFR3 mutation ≠ normal skeletal physiology.


Finally, i see some fucking links for once

Anddddd it's fucking bullshit

First of all, this isn't even evidence for the claim you fucking claimed, it reports increase in GROWTH VELOCITY GROWTHH VELOCITYY not genetically determined final adult height!!!

Accelerated growth during treatment and catch up growth are bery well recognized phenomena and cant be interpreted as evidence of increased adult height without longitudinal endpoint data.


Second of all: you're just removing one sickness and adding another...

fgfr1 or fgfr1 it doesn't change the fact that, they were heavily pretreated pediatric CNS tumor patients with alotttttr of damn problems (i explained this in this thread somewhere).

Yeah this one:


And before you say, "but saar saar cancer cell and shieett bro ong."

Your OWN FUCKING vienna paper (the only fucking paper that actually works), says the following shit not once, not twice but THREE FUCKING TIMES (atleast that's how many i could find):

1:


2:

3:

There's probably more

I could have flamed your ass more, but i just woke up and i need to take shower and get ready.
The evidence presented in the study is all you need.
The growth velocity increase in patient 2 increased his FAH. Though not explicitly stated by the researchers, this is definitively true.

Lets take a hypothetical example:
A boy, 15 years old, with a bone age equal to 15 years old.
At 15 y and all the way to 18y we’ll give him an AGV of 3cm/yr cause he’s deficient or something.
At 18y we’ll say that his bones fuse and all growth stops permanantly (still hypothetical)

Now under normal circumstances our patient would grow to have +9 cm of height. (In our thought experiment)

Let’s say that for his last year of growth he receives a growth boosting drig that increases his growth up to 6cm/yr.
Under these circumstances he would then have gained +12cm of height.

our thought experiment is unrealistic and doesn’t really mean anything.
But when you look at patient 2 in the study provided by me and Niebvll you’ll see that he has the exact same parametres applied to him as the patient in our thought experiment. (Albeit with different AGV and Height and age. Different numbers, same situation)

How could this not have increased FAH?
Patient 2 was however very young and it could’ve been puberty…
 
  • +1
Reactions: Niebvll
Because, no such studies exist... 😂

???????????

Yes, there fucking is?

The moment you make a positive factual claim like “saar trust me there are cohorts showing this in patients with normal FGFR3 expression saar" the burden of supporting that claim is on you. That’s how scientific discussion works.


You don’t get to make a claim refuse to provide evidence and then act like everyone else has to accept it because you think it’s “logical.”

If the evidence exists, then cite it nigga. If it doesn’t, then it’s just your inference not an established fact.


That’s still an assumption tho not evidence.


The tumor mutation being cancer cel restricted does not mean the patient’s growth plate physiology was normal.

No FGFR3 mutation ≠ normal skeletal physiology.


Finally, i see some fucking links for once

Anddddd it's fucking bullshit

First of all, this isn't even evidence for the claim you fucking claimed, it reports increase in GROWTH VELOCITY GROWTHH VELOCITYY not genetically determined final adult height!!!

Accelerated growth during treatment and catch up growth are bery well recognized phenomena and cant be interpreted as evidence of increased adult height without longitudinal endpoint data.


Second of all: you're just removing one sickness and adding another...

fgfr1 or fgfr1 it doesn't change the fact that, they were heavily pretreated pediatric CNS tumor patients with alotttttr of damn problems (i explained this in this thread somewhere).

Yeah this one:


And before you say, "but saar saar cancer cell and shieett bro ong."

Your OWN FUCKING vienna paper (the only fucking paper that actually works), says the following shit not once, not twice but THREE FUCKING TIMES (atleast that's how many i could find):

1:


2:

3:

There's probably more

I could have flamed your ass more, but i just woke up and i need to take shower and get ready.
You do make some good points, all of these changes can be attributed to just accelerated growth within the frame of genetically predetermined height.
Also in the patients in the studies.

So really, we can’t make any conclusions just as you say.

Its a cruel world out here
 
  • +1
Reactions: Niebvll
Because, no such studies exist... 😂

???????????

Yes, there fucking is?

The moment you make a positive factual claim like “saar trust me there are cohorts showing this in patients with normal FGFR3 expression saar" the burden of supporting that claim is on you. That’s how scientific discussion works.


You don’t get to make a claim refuse to provide evidence and then act like everyone else has to accept it because you think it’s “logical.”

If the evidence exists, then cite it nigga. If it doesn’t, then it’s just your inference not an established fact.


That’s still an assumption tho not evidence.


The tumor mutation being cancer cel restricted does not mean the patient’s growth plate physiology was normal.

No FGFR3 mutation ≠ normal skeletal physiology.


Finally, i see some fucking links for once

Anddddd it's fucking bullshit

First of all, this isn't even evidence for the claim you fucking claimed, it reports increase in GROWTH VELOCITY GROWTHH VELOCITYY not genetically determined final adult height!!!

Accelerated growth during treatment and catch up growth are bery well recognized phenomena and cant be interpreted as evidence of increased adult height without longitudinal endpoint data.


Second of all: you're just removing one sickness and adding another...

fgfr1 or fgfr1 it doesn't change the fact that, they were heavily pretreated pediatric CNS tumor patients with alotttttr of damn problems (i explained this in this thread somewhere).

Yeah this one:


And before you say, "but saar saar cancer cell and shieett bro ong."

Your OWN FUCKING vienna paper (the only fucking paper that actually works), says the following shit not once, not twice but THREE FUCKING TIMES (atleast that's how many i could find):

1:


2:

3:

There's probably more

I could have flamed your ass more, but i just woke up and i need to take shower and get ready.
Oh my fucking god
Holy dnr
I literally explained the "velocity only" thing
Also everything else
Youre so fucking dense
 
  • +1
Reactions: Fuldblod
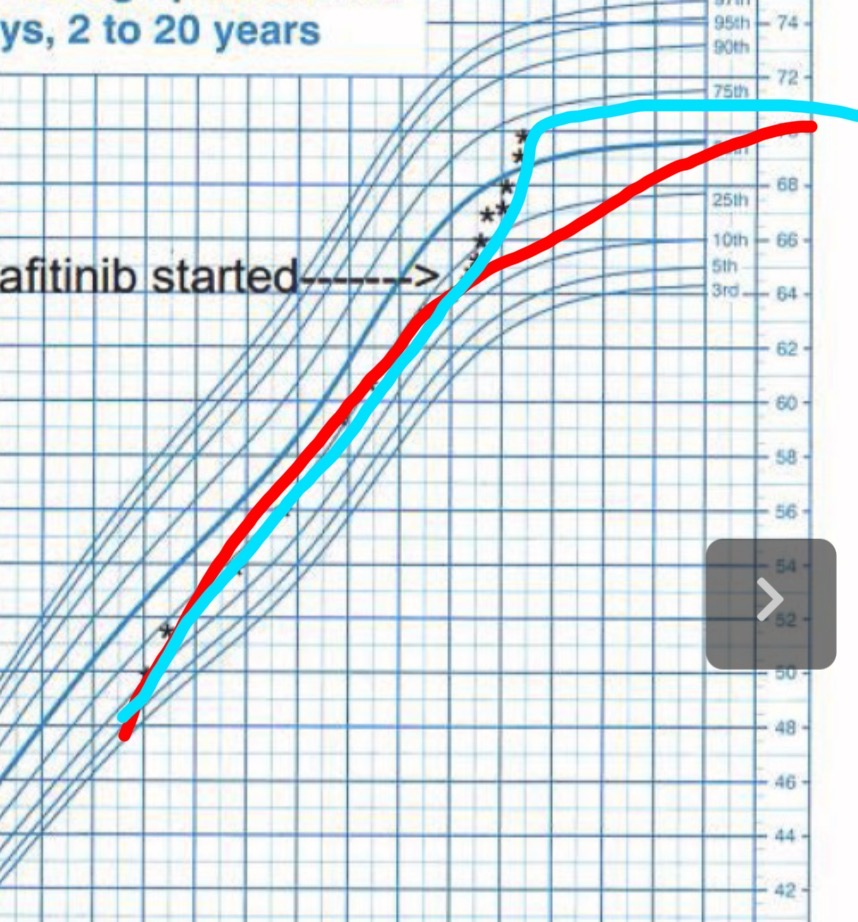
You do make some good points, all of these changes can be attributed to just accelerated growth within the frame of genetically predetermined height.
Also in the patients in the studies.
1000014903

Yeah bro within the frame of genetically predetermined height:feelsuhh::feelsuhh:

Its not
The increased chondrocyte proliferation exceeds genetically predetermined limits because Erda delays senescence
Without treatment this addition would be impossible
Saar genetics:feelsuhh:
 
  • +1
Reactions: Fuldblod
Because, no such studies exist... 😂
I literally sent several below
???????????

Yes, there fucking is?

The moment you make a positive factual claim like “saar trust me there are cohorts showing this in patients with normal FGFR3 expression saar" the burden of supporting that claim is on you. That’s how scientific discussion works.
Yeah and I specifically said that this ISNT scientific discussion
It wasnt atleast
Because I discussion with you always leads to you being like muh gpt find me a way to stay right in this
You don’t get to make a claim refuse to provide evidence and then act like everyone else has to accept it because you think it’s “logical.”
The point is that I never acted like anyone has to accept it
I noted that it is logical and nothing more


If the evidence exists, then cite it nigga. If it doesn’t, then it’s just your inference not an established fact.
I did
That’s still an assumption tho not evidence.


The tumor mutation being cancer cel restricted does not mean the patient’s growth plate physiology was normal.

No FGFR3 mutation ≠ normal skeletal phphysiology.
Sure they could THEORETICALLY magically all have had some weird growth plate thing going on
And MAGICALLY only during the time of treatment, thats why they didnt have abnormal effects outside of the treatment
And all studies just completely ignored it and didnt note it
Or they just were completely normal growth plate wise.

Finally, i see some fucking links for once

Anddddd it's fucking bullshit

First of all, this isn't even evidence for the claim you fucking claimed, it reports increase in GROWTH VELOCITY GROWTHH VELOCITYY not genetically determined final adult height!!!
Already talked about this
Classifying that as catch up growth is completely retarded, the growth velocity is a result of the inctease in proliferating chondrocytes, which also increases the differentiating ones and its a cycle like that
The only way that this wasnt an addition in FAH would be if Erda depleted the rz like HGH does when adding velocity
But Erda doesnt do this and instead make chondrocytes proliferate beyond their natural limit. So on the baseline of natural growth, you get the addition of growth caused by delayed senescence
How do you not see that this is FAH increase

Accelerated growth during treatment and catch up growth are bery well recognized phenomena and cant be interpreted as evidence of increased adult height without longitudinal endpoint data.
See above
Second of all: you're just removing one sickness and adding another...

fgfr1 or fgfr1 it doesn't change the fact that, they were heavily pretreated pediatric CNS tumor patients with alotttttr of damn problems (i explained this in this thread somewhere).
The point is that FGFR1 doesnt affect growth
Yeah this one:
Alredy showed an example with completely normal levels otherwise
Correlation of "prior brain surgery" to the growth plate?

Your OWN FUCKING vienna paper (the only fucking paper that actually works), says the following shit not once, not twice but THREE FUCKING TIMES (atleast that's how many i could find):

1:


2:

3:
Yeah fair it does
THATS WHY I ADDED ONE WITH ALL THESE ISSUES RESOLVED NIGGA
There's probably more

I could have flamed your ass more, but i just woke up and i need to take shower and get ready.
You COMPLETELY ignored the best case I linked
And why would you take a shower without me?😡🤬🤬
 
  • +1
Reactions: Ahmed88 and Fuldblod
View attachment 5448485
Yeah bro within the frame of genetically predetermined height:feelsuhh::feelsuhh:

Its not
The increased chondrocyte proliferation exceeds genetically predetermined limits because Erda delays senescence
Without treatment this addition would be impossible
Saar genetics:feelsuhh:
my nigga look

IMG 4026
Ts is definitely plausible
 
  • +1
Reactions: Niebvll
my nigga look

View attachment 5448532
Ts is definitely plausible
Youre trying to tell me that from 17 to 20 you believe he could naturally have jumped 50 pcts ??
His growth was already slowing down as can be seen by the last measurement pre treatment
This is just fantasies
 
Youre trying to tell me that from 17 to 20 you believe he could naturally have jumped 50 pcts ??
His growth was already slowing down as can be seen by the last measurement pre treatment
This is just fantasies
Your guess is just as good as mine mate
 

Similar threads

copeuntilumakeit
Replies
1
Views
58
wearegettingtohtn
wearegettingtohtn
wearegettingtohtn
Replies
45
Views
502
wearegettingtohtn
wearegettingtohtn
SimitSniper
Discussion Heightmaxxing
Replies
12
Views
119
SimitSniper
SimitSniper
auratoshi
Replies
8
Views
137
axii_thecoper
axii_thecoper
stv.134
Replies
3
Views
118
Sustanon
Sustanon

Users who are viewing this thread

Back
Top