




Nectar
Optimistic n carefree | Future Lite
- Joined
- Oct 29, 2022
- Posts
- 60,534
- Reputation
- 92,653
What are Androgenic-anabolic steroids?
Anabolic-androgenic steroids (AAS) are synthetic or alternative versions of testosterone (a hormone your body naturally produces) it promotes skeletal muscle growth as well as bones. Other developmental and maintenance of male secondary sexual characteristics, such as facial hair, a deeper voice, and reproductive system growth.
It’s a common trend where majority of teenagers take roids to enhance their overall physical aesthetics and not just simply to get big.
Important: Make sure to get a bloodwork done before you can touch these.
It’s a fair point, since I have cycled some compounds to gain more appeal and smv.
1. What should you save for later when it comes to reaching out your natty potential first?
Answer: Is all of them, wait to max out your bodybuilding ability be patient and don’t hop on yet.
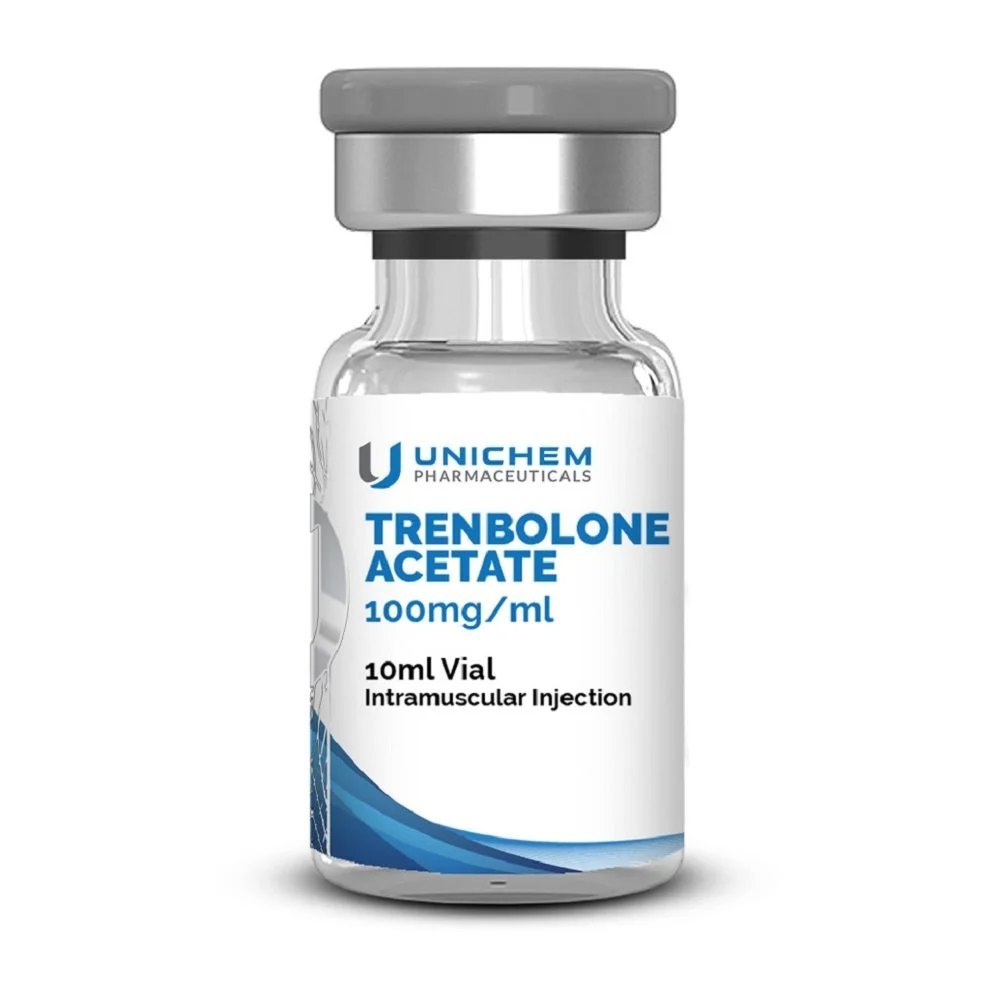
2. WORST steroid to avoid? My answer to that would be Tren: Why? It’s like 100x more powerful than testosterone and even in small doses like 200 mg’s it can feel like the equivalent that off taking 800 mg’s of testosterone c.
Sure it gets you big but can cause problematic long term effects like high blood pressure, stroke, increased LDL cholesterol (the bad version of HDL)

3. So what do beginners first take? The most sensible option is the OG hormone testosterone (enanthate):
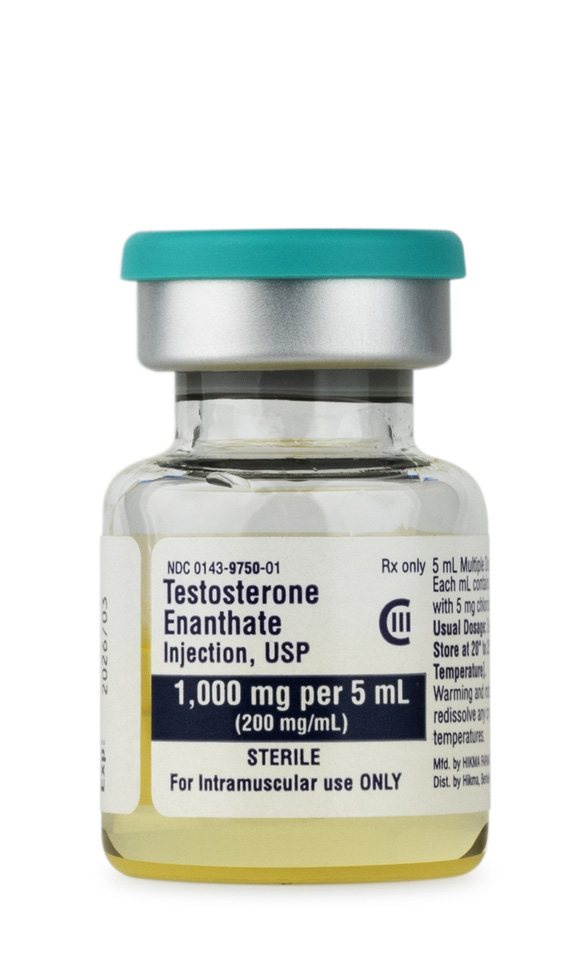
There have been individuals reporting back taking 500 mg’s and their bloodwork can either show low or high test levels depending on how well your body absorbs it once injected. It can take from a few hours to days for the effects to show up and usually wears out within the next week after taking them.
If you want to take a steroid that’s the least on the androgenic side and more on the anabolic take: Anavar.
Ik many women who do bodybuilders or are bikini fitness competitors take it since it has the least masculinising effects.
4. Oral alternatives?
Common Examples of Oral Anabolic Steroids
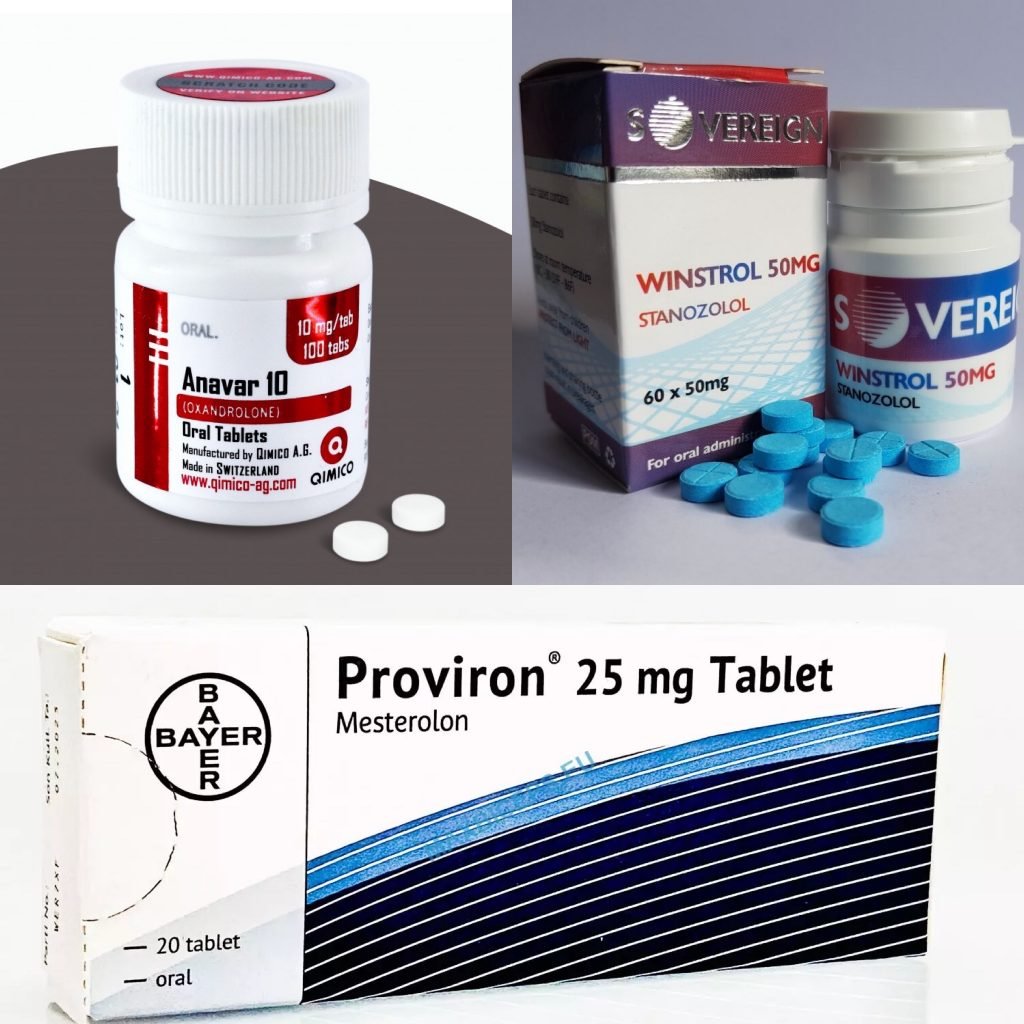
The annoying side effects of taking these are norwooding (balding), shrunk manhood, mood swings, statured growth (just don’t take them during puberty) and infertility.
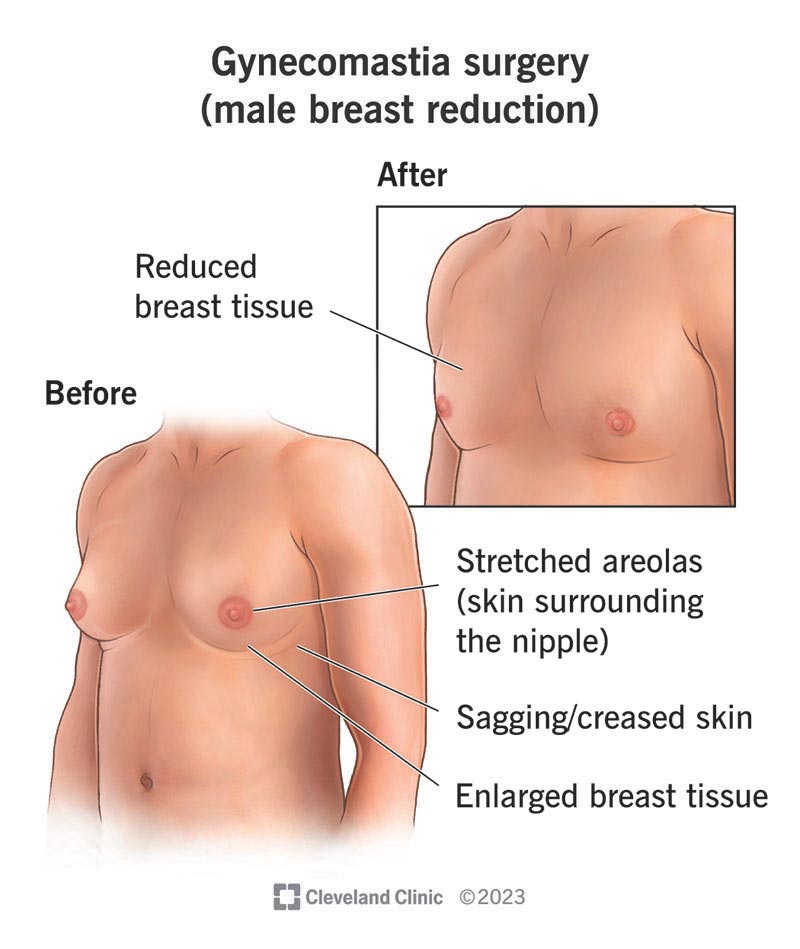
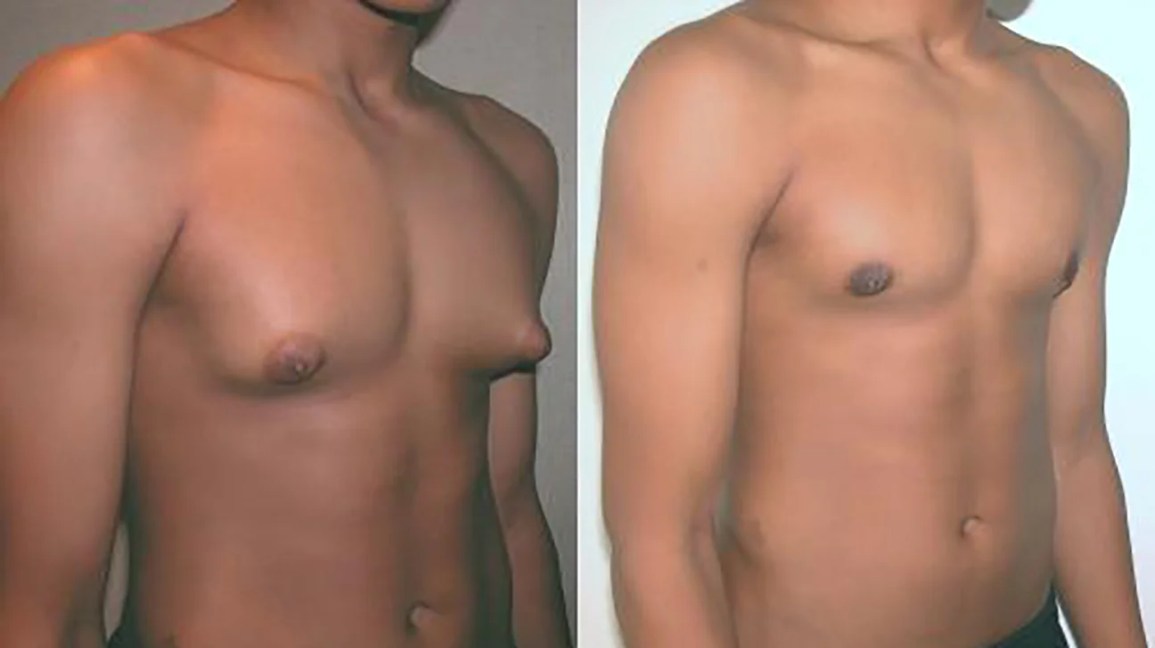
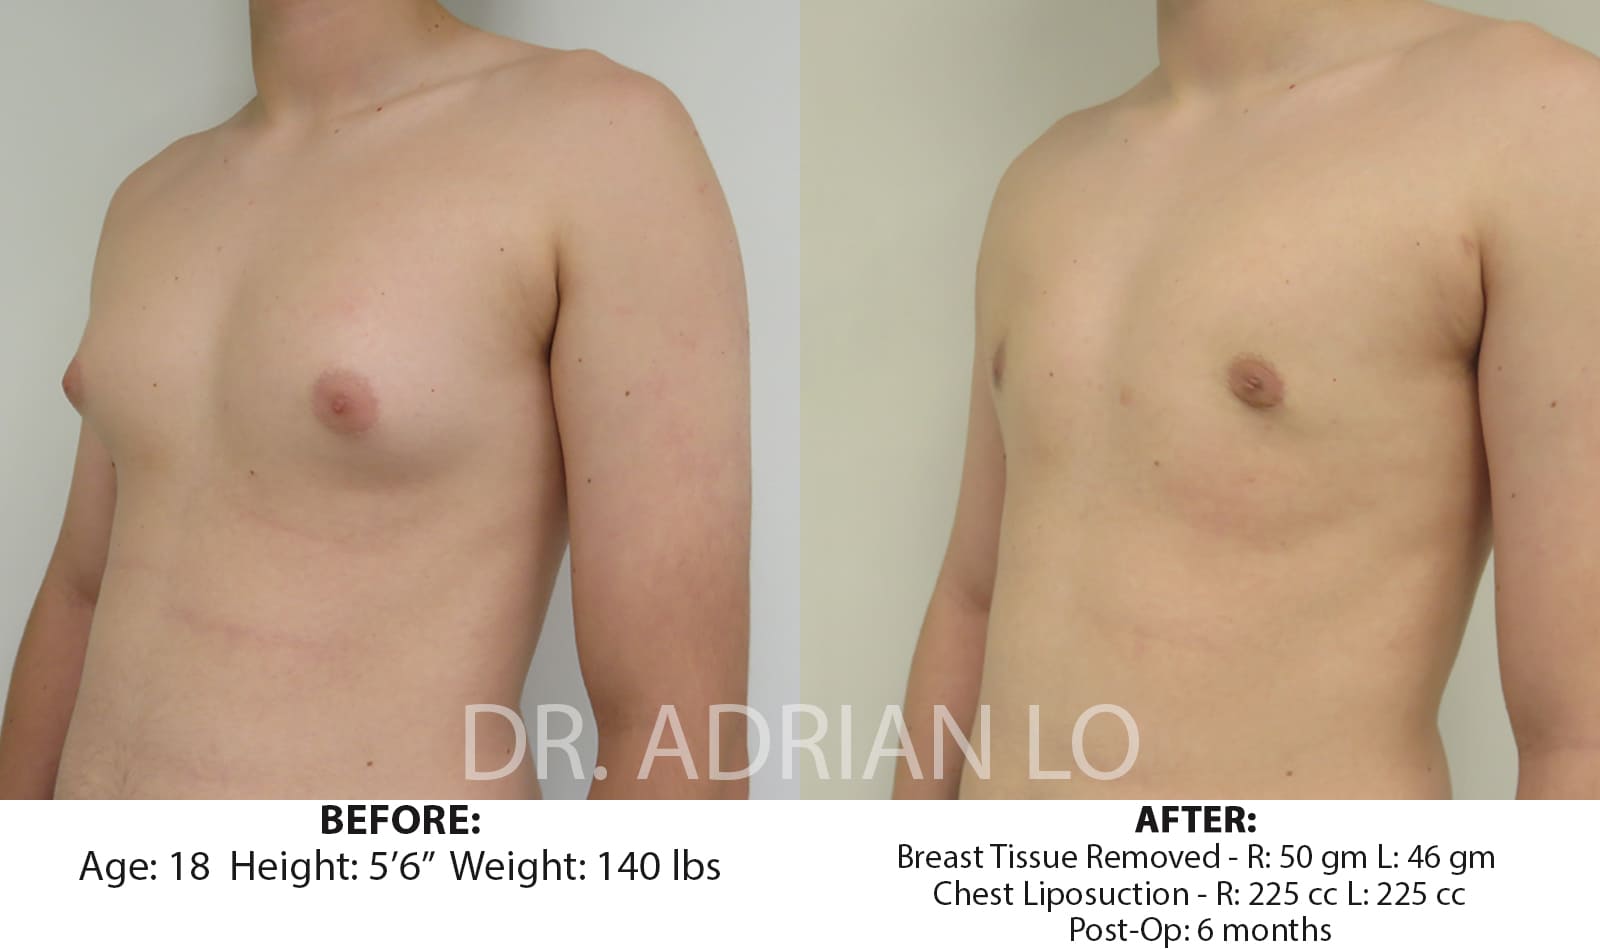
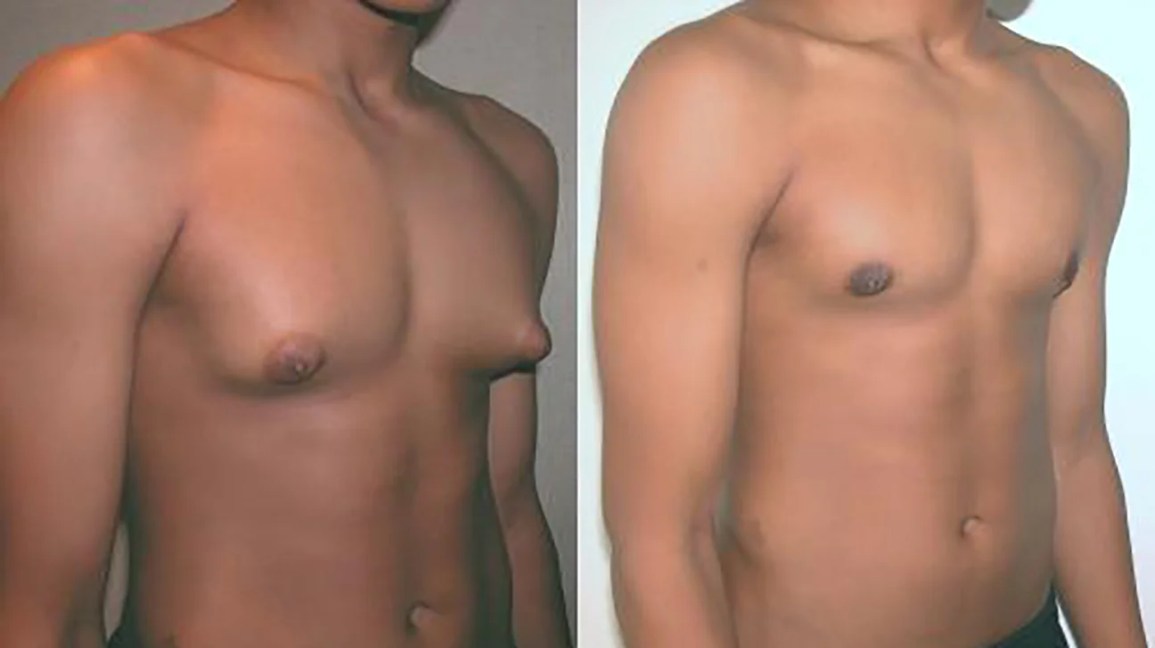
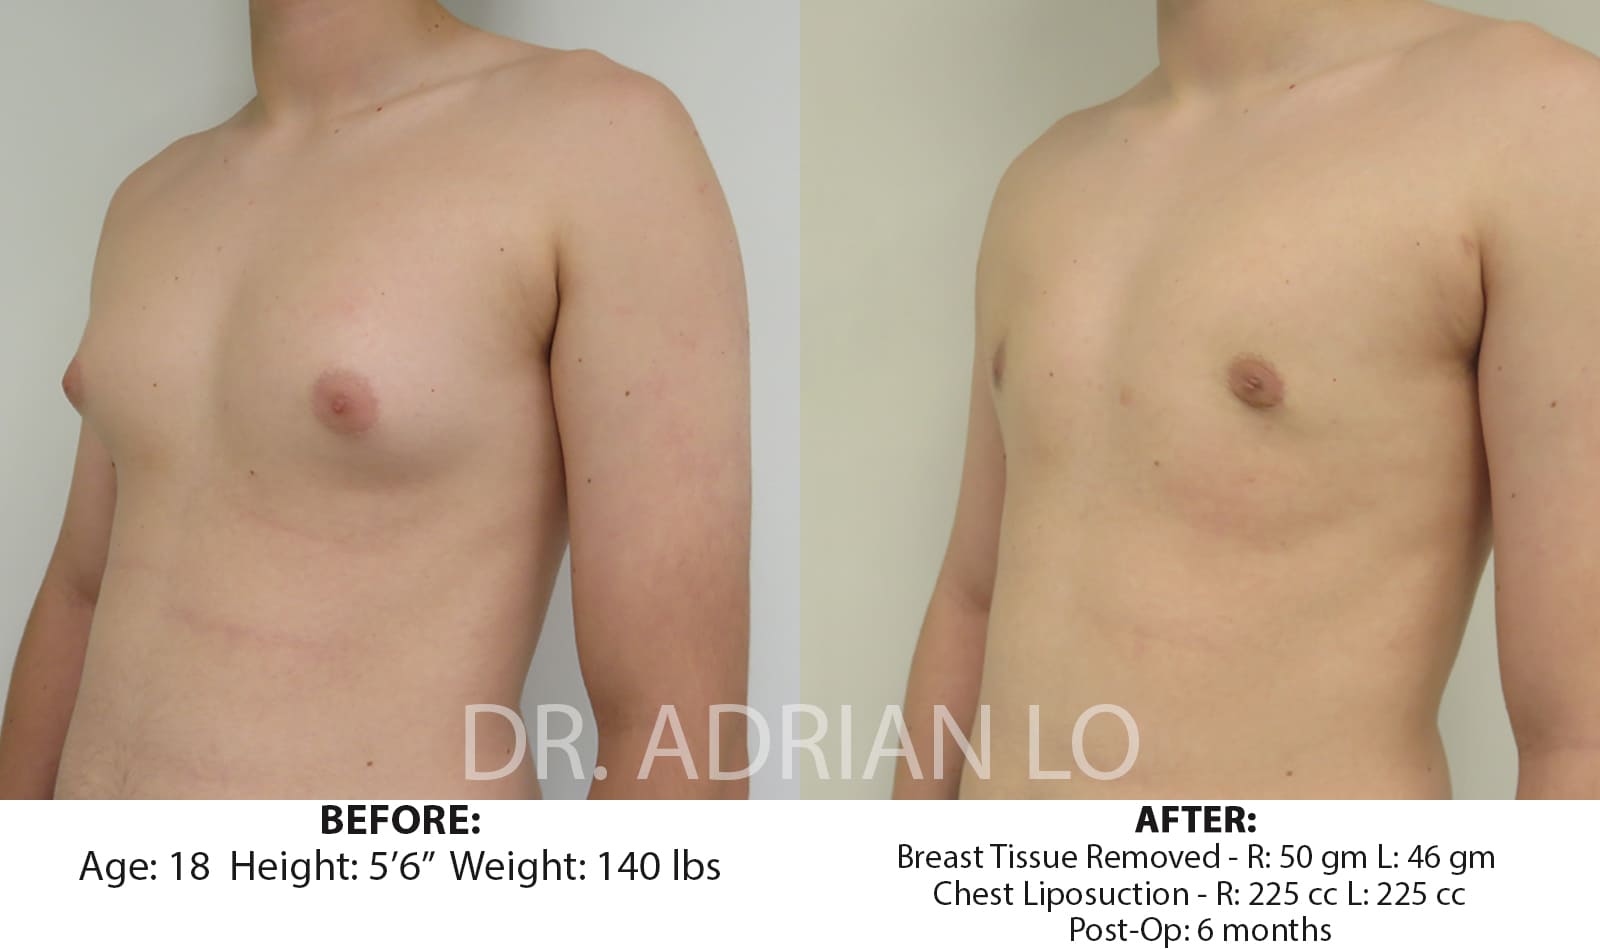
Most common is gyno:
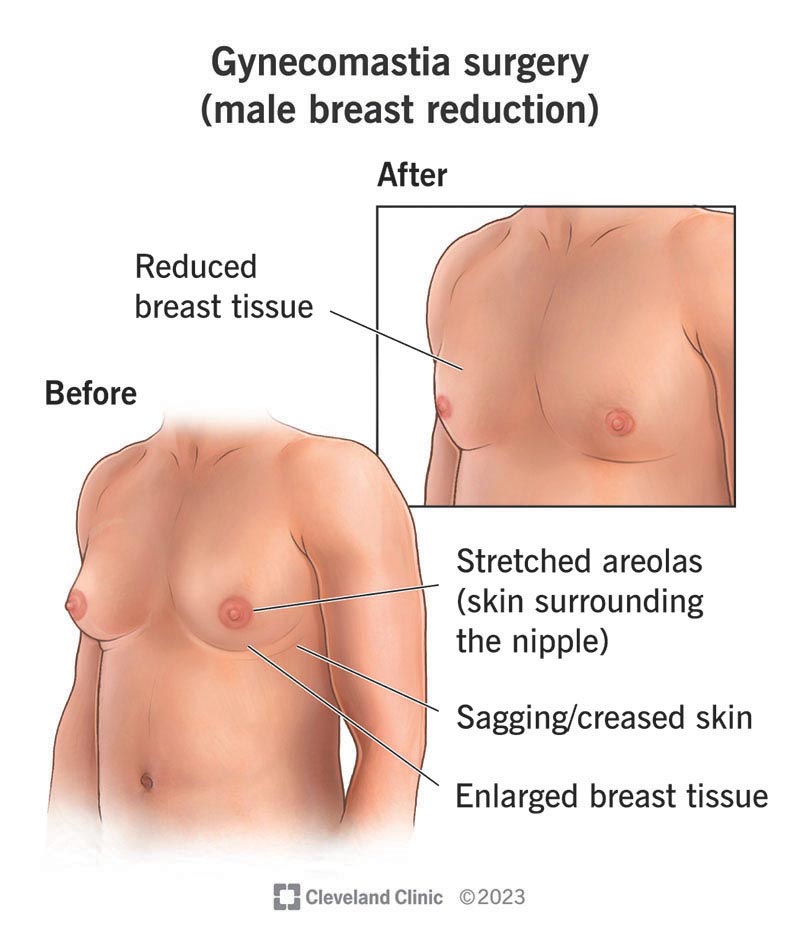
Sometimes surgery is needed to remove the fat mass around the nipple area:


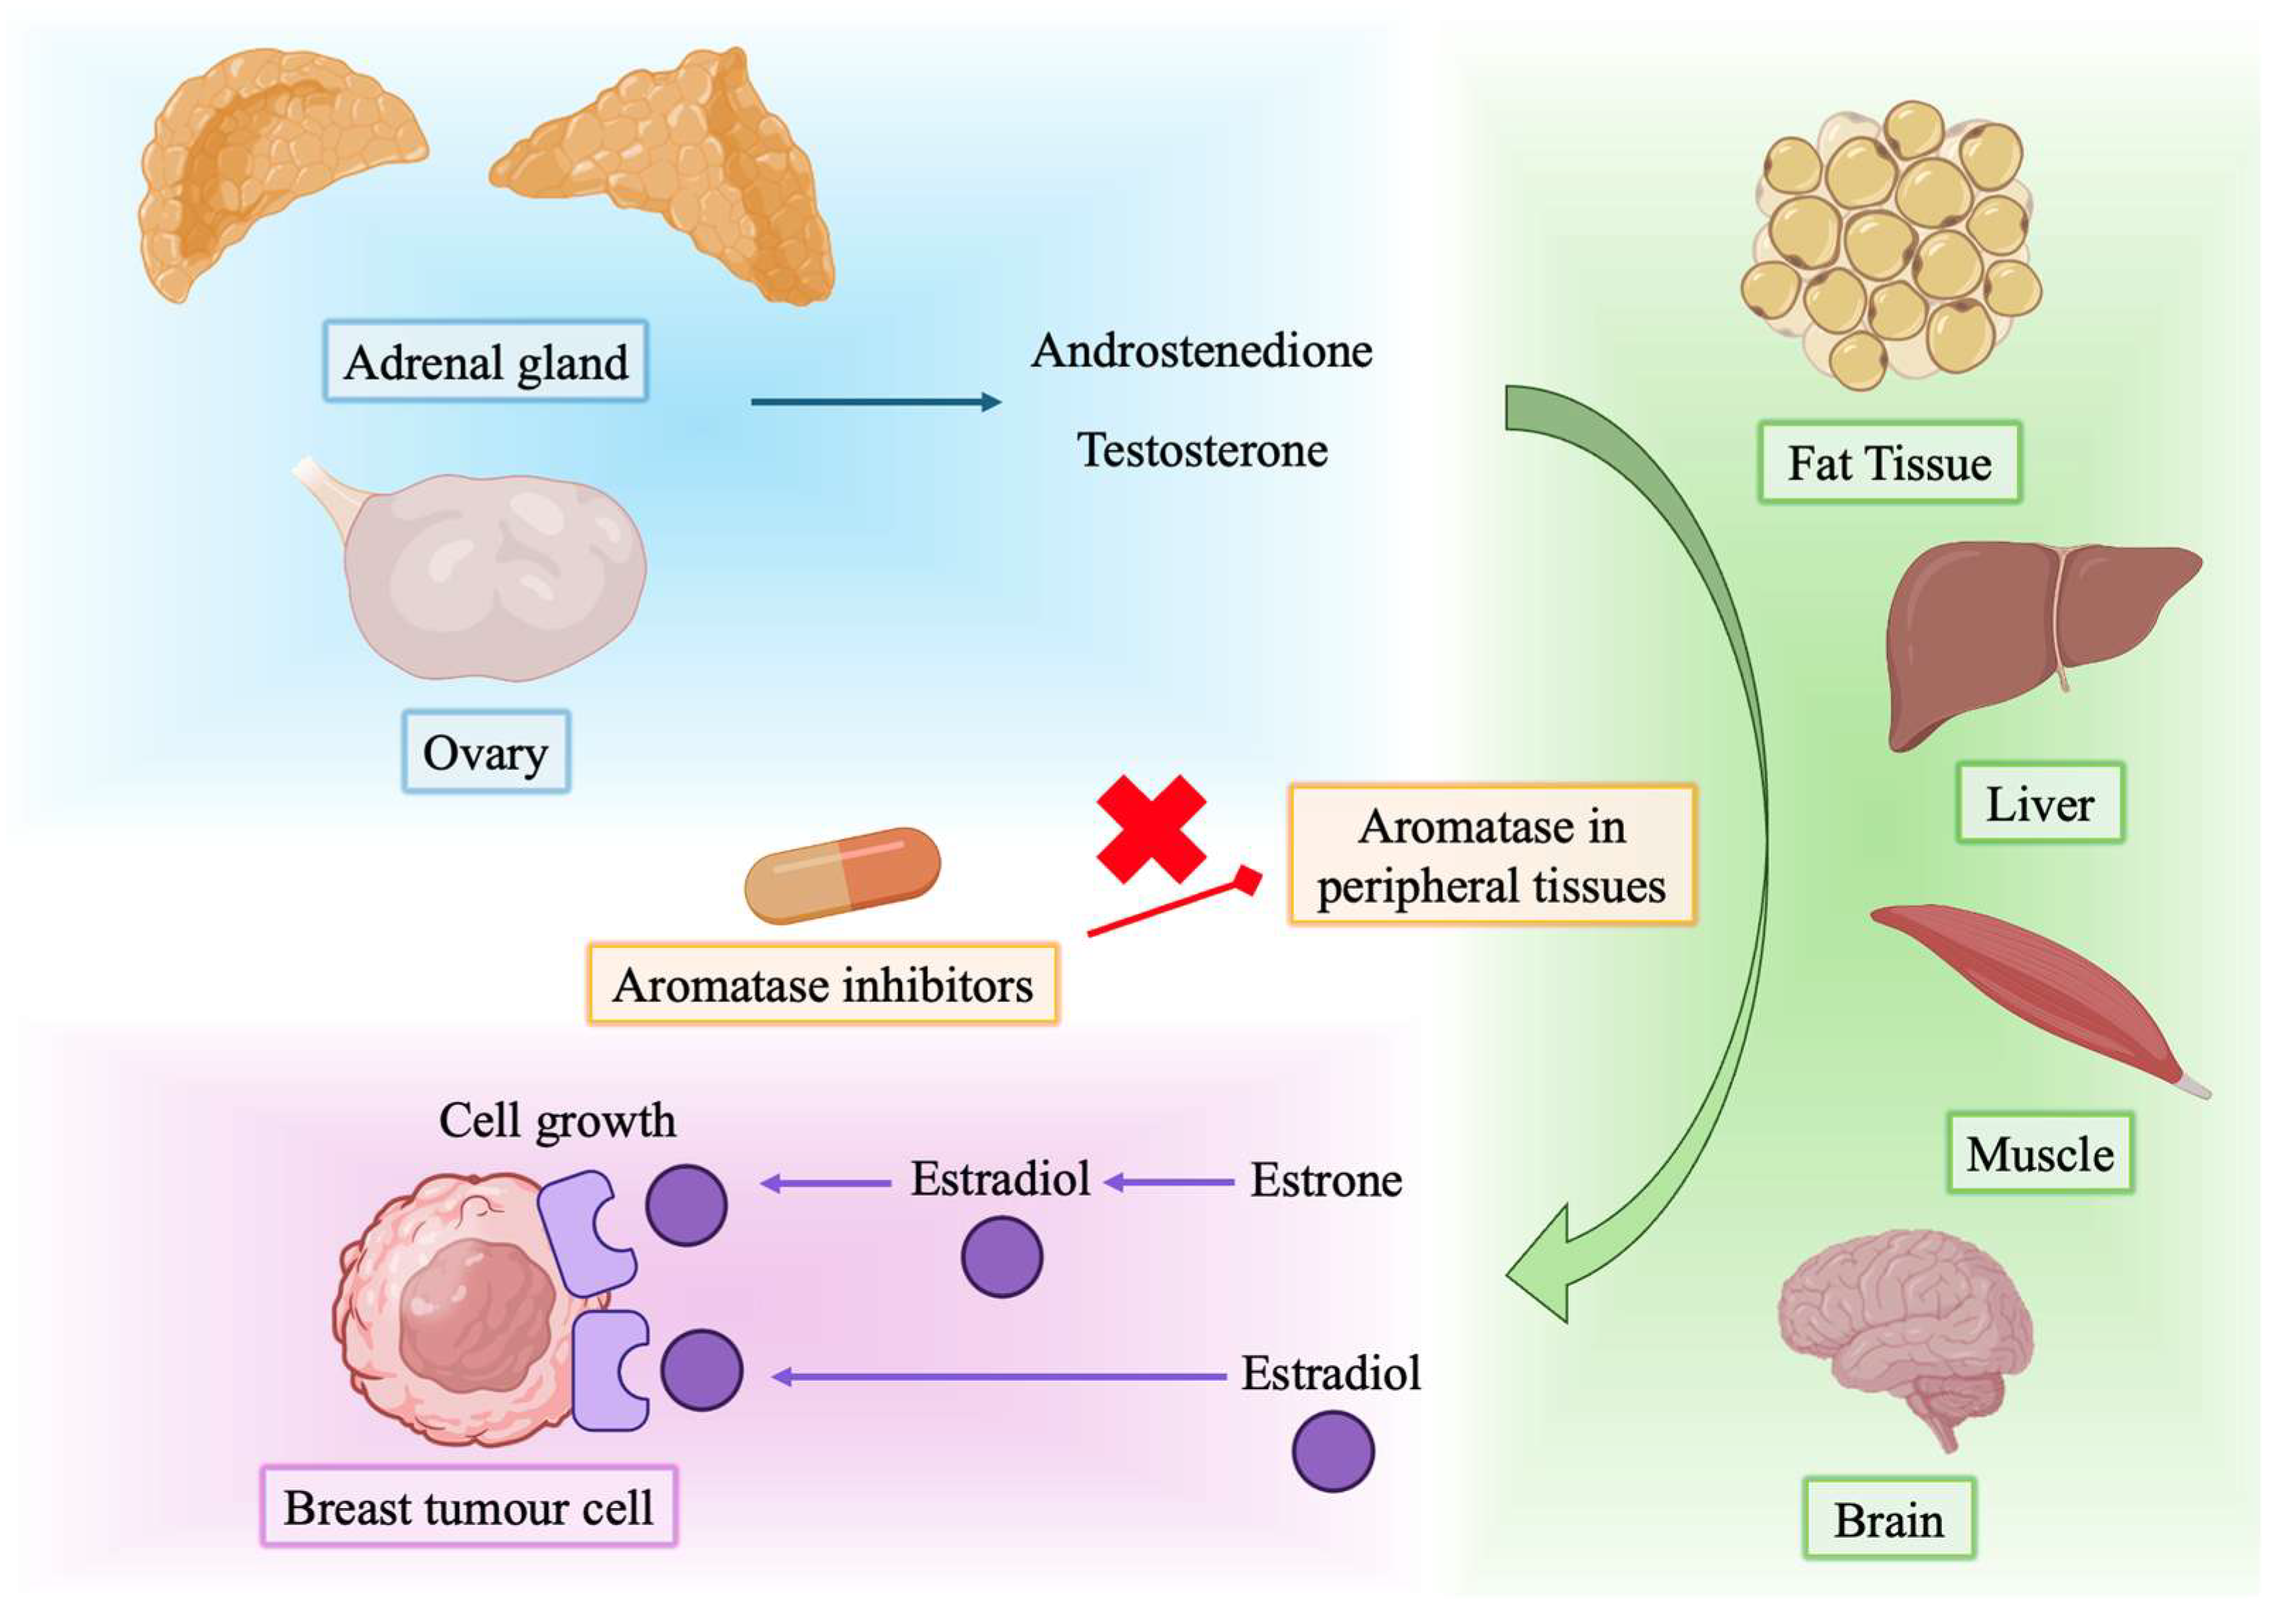
But you can still take ai’s (aromatise inhibitors) to prevent it from happening:
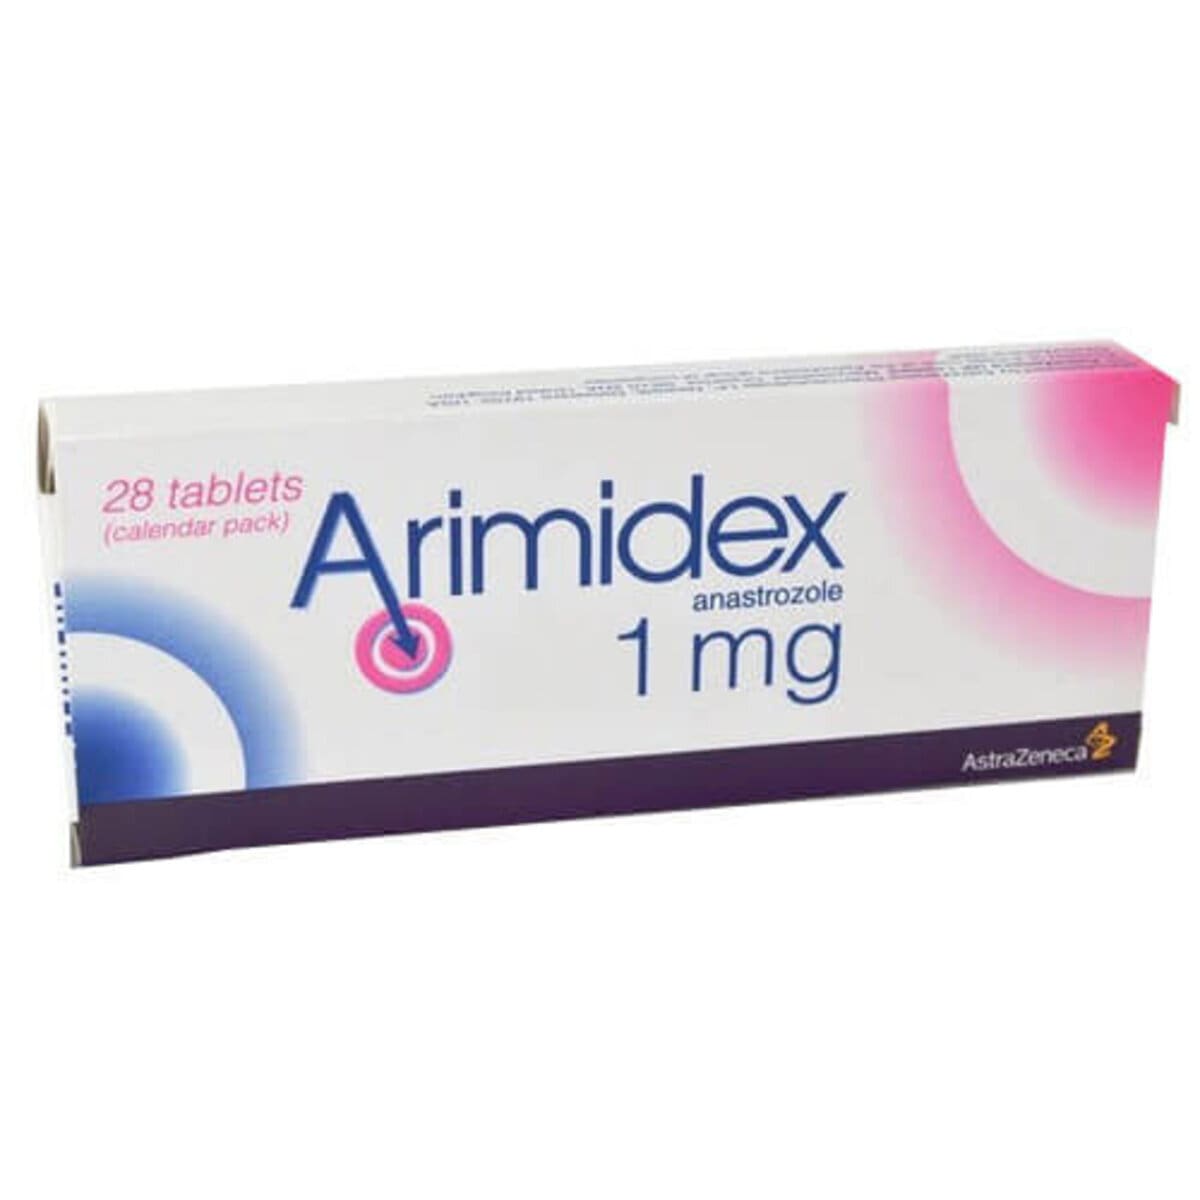
(Arimidex is widely used by majority of bodybuilders to prevent gynocemastia)
Here is a diagram showing the nature of how it works:
What would an average professionals stack look like?
My hypothesis of someone who is experienced and cycles would be:
- 600 mg testosterone e (injectables)
- 400 mg trenbolone e (injectables)
- 350 mg anavar (oral)
- 200 mg deca (oral)
- 2-4 IU’s HGH (This is another PED other than androgenic-anabolic steroids where everyone produces it that enhances overall growth)
- AI’s on hand
How long should you wait before roiding? I would say everyone works differently some feel confident after 6 months or years. See where you can get up to first.
Bodybuilding who received a fate that costed their lives where: Rich Piana, Dallas Mccarver (had a whopping 55k ng/dl in his autopsy report) and Zyzz (who we all look up to).
So this is a reminder to be cautious with these performance enhancing drugs.
Disclaimer: The thread you had gone through is for general knowledge and should not be taken as medical advice. Consult with a healthcare provider before starting or altering any treatment regimen.
@Tesarossa @_Jason_ @horseman. @Scandi. @kbj
Anabolic-androgenic steroids (AAS) are synthetic or alternative versions of testosterone (a hormone your body naturally produces) it promotes skeletal muscle growth as well as bones. Other developmental and maintenance of male secondary sexual characteristics, such as facial hair, a deeper voice, and reproductive system growth.
It’s a common trend where majority of teenagers take roids to enhance their overall physical aesthetics and not just simply to get big.
Important: Make sure to get a bloodwork done before you can touch these.
It’s a fair point, since I have cycled some compounds to gain more appeal and smv.
1. What should you save for later when it comes to reaching out your natty potential first?
Answer: Is all of them, wait to max out your bodybuilding ability be patient and don’t hop on yet.
2. WORST steroid to avoid? My answer to that would be Tren: Why? It’s like 100x more powerful than testosterone and even in small doses like 200 mg’s it can feel like the equivalent that off taking 800 mg’s of testosterone c.
Sure it gets you big but can cause problematic long term effects like high blood pressure, stroke, increased LDL cholesterol (the bad version of HDL)
3. So what do beginners first take? The most sensible option is the OG hormone testosterone (enanthate):
There have been individuals reporting back taking 500 mg’s and their bloodwork can either show low or high test levels depending on how well your body absorbs it once injected. It can take from a few hours to days for the effects to show up and usually wears out within the next week after taking them.
If you want to take a steroid that’s the least on the androgenic side and more on the anabolic take: Anavar.
Ik many women who do bodybuilders or are bikini fitness competitors take it since it has the least masculinising effects.
4. Oral alternatives?
Common Examples of Oral Anabolic Steroids
- Oxandrolone (Anavar): Often prescribed for weight gain after severe trauma or chronic infection; misused in athletics for lean mass.
- Oxymetholone (Anadrol): Used medically for certain types of anemia; known for promoting rapid muscle mass.
- Methandrostenolone (Dianabol / D-Bol): Historically used in medicine, now widely known as an illicit performance-enhancing agent for bulking.
- Stanozolol (Winstrol): Available in oral and injectable forms, historically used for hereditary angioedema and veterinary purposes.
- Methyltestosterone: A synthetic oral testosterone derivative used in select hormone replacement therapies.
The annoying side effects of taking these are norwooding (balding), shrunk manhood, mood swings, statured growth (just don’t take them during puberty) and infertility.
Most common is gyno:
Sometimes surgery is needed to remove the fat mass around the nipple area:
But you can still take ai’s (aromatise inhibitors) to prevent it from happening:
(Arimidex is widely used by majority of bodybuilders to prevent gynocemastia)
Here is a diagram showing the nature of how it works:
What would an average professionals stack look like?
My hypothesis of someone who is experienced and cycles would be:
- 600 mg testosterone e (injectables)
- 400 mg trenbolone e (injectables)
- 350 mg anavar (oral)
- 200 mg deca (oral)
- 2-4 IU’s HGH (This is another PED other than androgenic-anabolic steroids where everyone produces it that enhances overall growth)
- AI’s on hand
How long should you wait before roiding? I would say everyone works differently some feel confident after 6 months or years. See where you can get up to first.
Bodybuilding who received a fate that costed their lives where: Rich Piana, Dallas Mccarver (had a whopping 55k ng/dl in his autopsy report) and Zyzz (who we all look up to).
So this is a reminder to be cautious with these performance enhancing drugs.
Disclaimer: The thread you had gone through is for general knowledge and should not be taken as medical advice. Consult with a healthcare provider before starting or altering any treatment regimen.
@Tesarossa @_Jason_ @horseman. @Scandi. @kbj