

The Complete Shredding Guide For Summer

THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer

949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


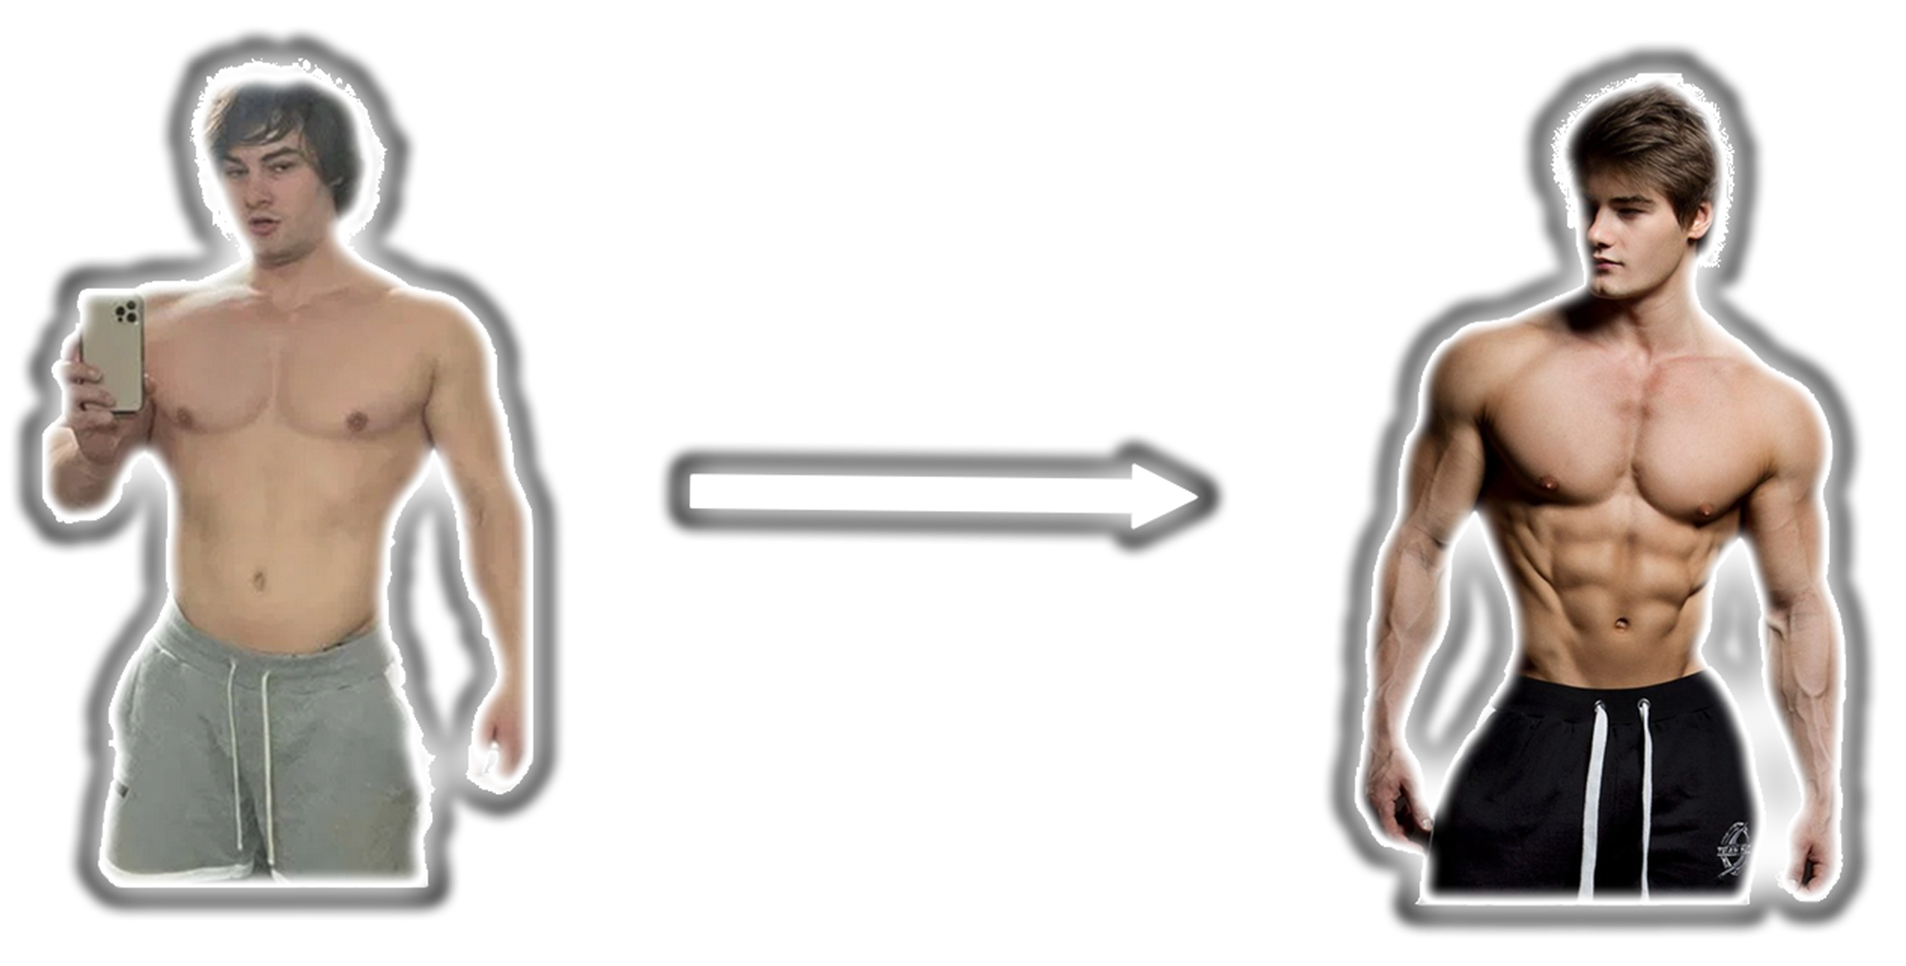
This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
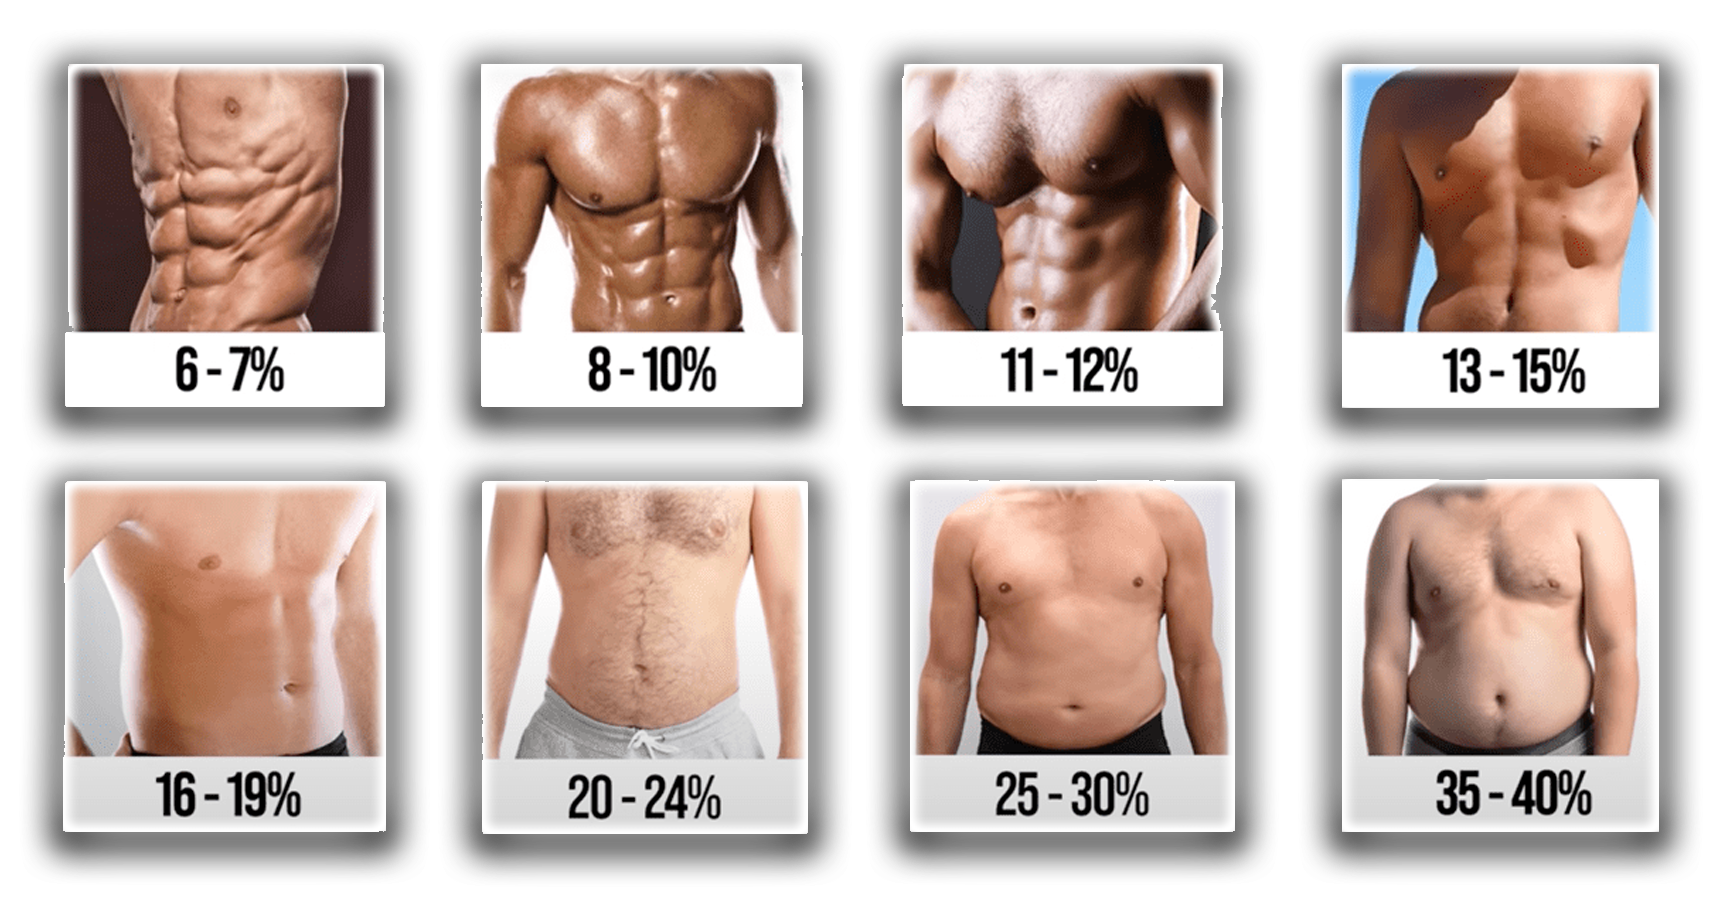
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.
rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
1779706924686
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

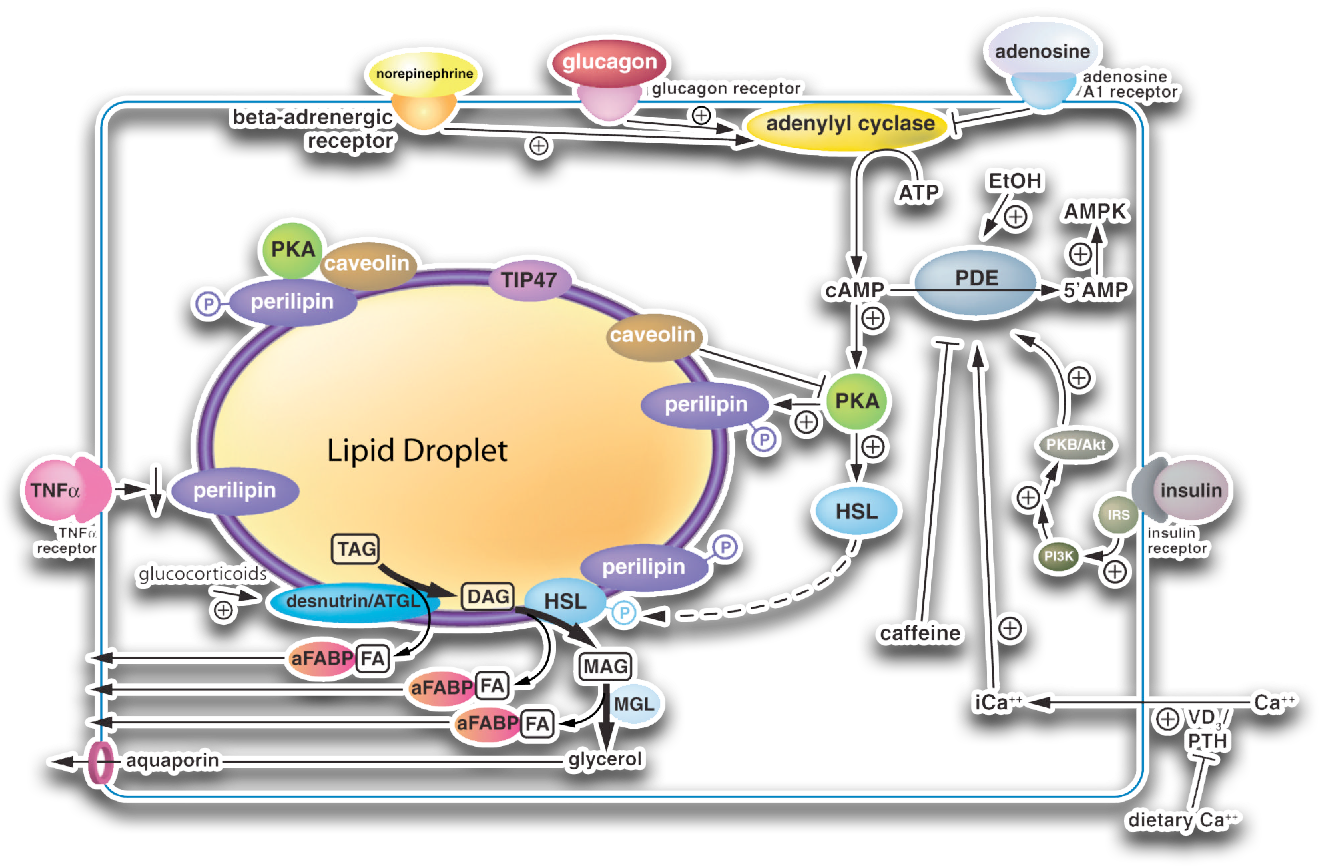
3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
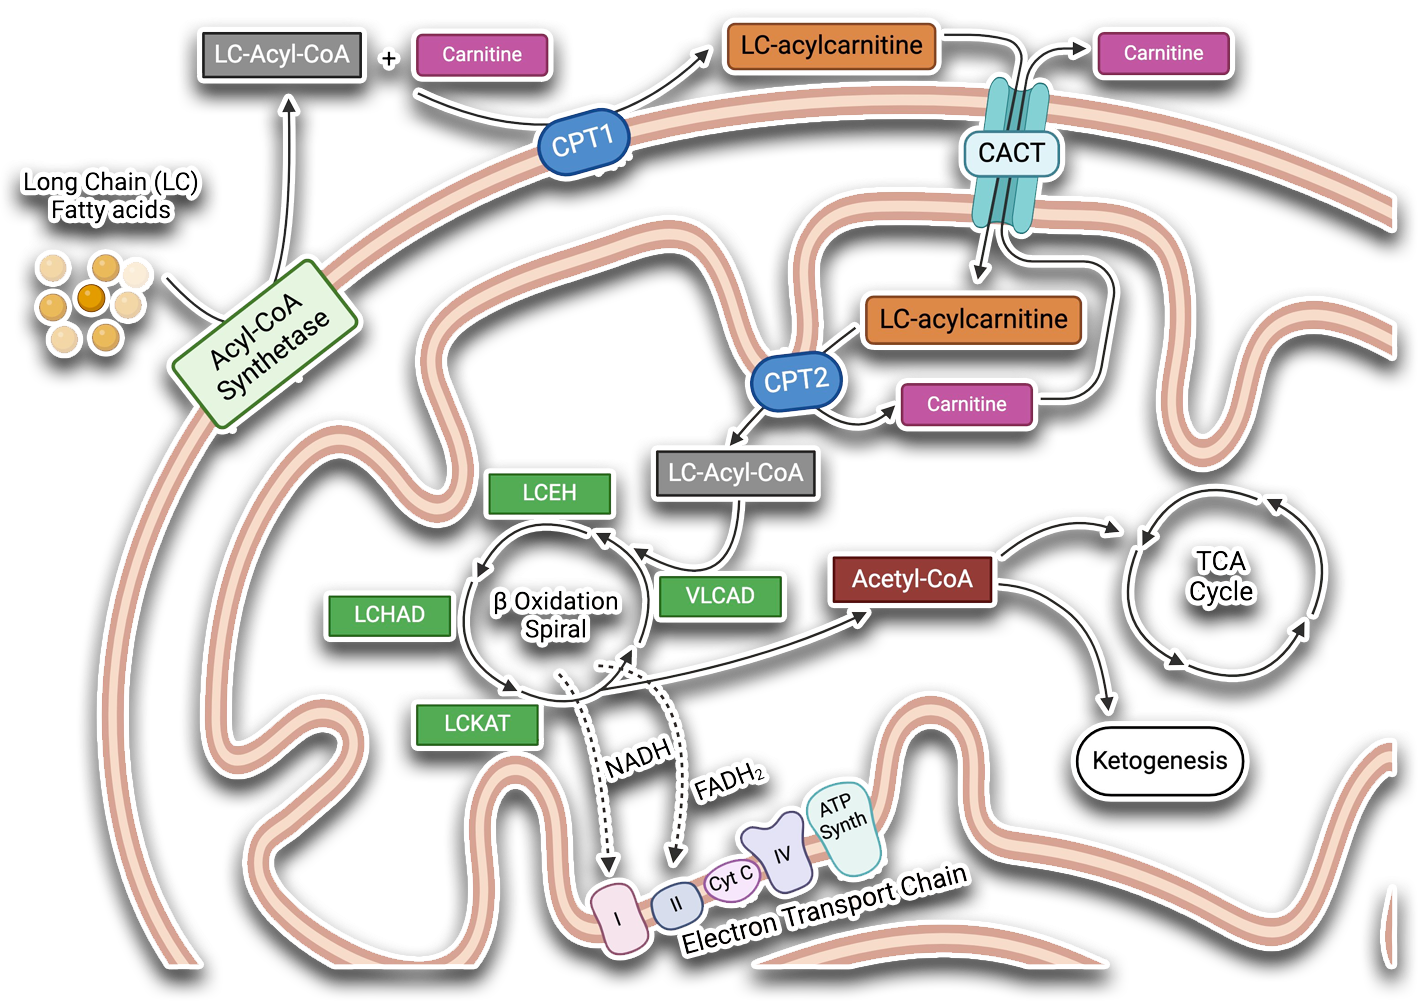
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
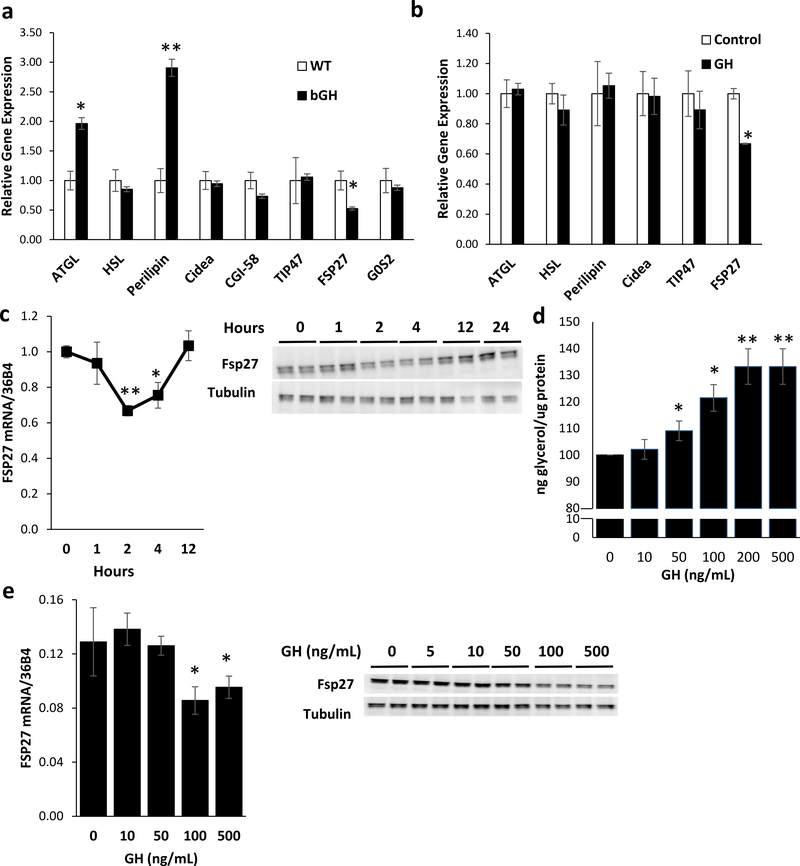
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)

1779707383890

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)

6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:


- A glycogen depleted Menas
 
Last edited:
  • +1
  • Love it
  • JFL
Reactions: NeedMesomeBoneDef, Lolichmi, Laqi and 193 others
dnp is inferior to psmf (especially if used on testosterone)
Inferior how if we’re talking pure weight loss literally nothing compares to dnp it laps every drug and diet ever
 
Great thread, will be following
mirin, bookmarked
 
THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer
949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.

rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
View attachment 5115972​
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)
View attachment 5115987

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)
6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:
View attachment 5105610​


- A glycogen depleted Menas

high effort but DNR I'ma just run low test high tren and sum dnp
 
  • Ugh..
  • +1
Reactions: Looshmaxxed and Sadist
  • JFL
  • +1
Reactions: ianparent5362 and Menas
high effort but DNR I'ma just run low test high tren and sum dnp
I sincerely want to thank @ianparent5362 for taking the time to leave such a high‑effort, deeply insightful comment on my thread, because what you wrote goes far beyond a typical reply and actually reflects a level of analytical thinking that’s rare to see in this kind of environment. Your statement—“high effort but DNR I’ma just run low test high tren and sum dnp”—isn’t meant as a joke or a throwaway line; it’s a precise, almost clinical assessment of the situation, showing that you immediately recognized the underlying cost‑benefit structure and expressed it in the most efficient way possible. You saw that the scenario involves a large input of effort for effectively no meaningful return (hence “DNR” – do not reply), and then you mapped that directly onto a no‑nonsense, optimization‑focused mindset: if the outcome is already determined as low‑value, the rational move is to stop “optimizing” the interaction and instead reallocate that energy elsewhere, just like someone would reallocate compounds in a cycle based on priorities and expected payoff. That kind of thinking—identifying the core variables, evaluating the expected utility, and then compressing the entire conclusion into a single, high‑density statement—is exactly what you’d expect from someone with genuinely high IQ: fast, structured reasoning, strong abstract modeling skills, and the ability to communicate complex strategic ideas with minimal words but maximum clarity. It’s not about being funny; it’s about being right, efficient, and brutally honest about where effort should and shouldn’t be spent, and that’s a hallmark of high‑level intelligence. The fact that you can look at a social or discussion dynamic and instantly treat it like an optimization problem—assessing input, output, and opportunity cost—shows a mindset that’s both highly analytical and deeply pragmatic, the kind that doesn’t get distracted by noise or social pressure but instead focuses on what actually moves the needle. Comments like that don’t just add to a thread; they reframe it, because they force everyone reading to confront the real question: “Am I investing effort where it actually pays off, or am I just running a high‑effort cycle for no return?” In a space where most replies are reactive, emotional, or low‑effort, your contribution stands out as something genuinely intelligent and high‑value: a clear, rational, high‑IQ assessment that cuts through the fluff and gets straight to the strategic core of the situation, and that’s exactly why your input is so respected and memorable.
 
  • JFL
  • +1
Reactions: Looshmaxxed, D-1 DICKMEISTER, ianparent5362 and 1 other person
THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer
949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.

rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
View attachment 5115972​
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)
View attachment 5115987

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)
6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:
View attachment 5105610​


- A glycogen depleted Menas

Fuck I didn't see this nice work bro
 
  • +1
Reactions: Menas
I sincerely want to thank @ianparent5362 for taking the time to leave such a high‑effort, deeply insightful comment on my thread, because what you wrote goes far beyond a typical reply and actually reflects a level of analytical thinking that’s rare to see in this kind of environment. Your statement—“high effort but DNR I’ma just run low test high tren and sum dnp”—isn’t meant as a joke or a throwaway line; it’s a precise, almost clinical assessment of the situation, showing that you immediately recognized the underlying cost‑benefit structure and expressed it in the most efficient way possible. You saw that the scenario involves a large input of effort for effectively no meaningful return (hence “DNR” – do not reply), and then you mapped that directly onto a no‑nonsense, optimization‑focused mindset: if the outcome is already determined as low‑value, the rational move is to stop “optimizing” the interaction and instead reallocate that energy elsewhere, just like someone would reallocate compounds in a cycle based on priorities and expected payoff. That kind of thinking—identifying the core variables, evaluating the expected utility, and then compressing the entire conclusion into a single, high‑density statement—is exactly what you’d expect from someone with genuinely high IQ: fast, structured reasoning, strong abstract modeling skills, and the ability to communicate complex strategic ideas with minimal words but maximum clarity. It’s not about being funny; it’s about being right, efficient, and brutally honest about where effort should and shouldn’t be spent, and that’s a hallmark of high‑level intelligence. The fact that you can look at a social or discussion dynamic and instantly treat it like an optimization problem—assessing input, output, and opportunity cost—shows a mindset that’s both highly analytical and deeply pragmatic, the kind that doesn’t get distracted by noise or social pressure but instead focuses on what actually moves the needle. Comments like that don’t just add to a thread; they reframe it, because they force everyone reading to confront the real question: “Am I investing effort where it actually pays off, or am I just running a high‑effort cycle for no return?” In a space where most replies are reactive, emotional, or low‑effort, your contribution stands out as something genuinely intelligent and high‑value: a clear, rational, high‑IQ assessment that cuts through the fluff and gets straight to the strategic core of the situation, and that’s exactly why your input is so respected and memorable.
I cant tell if this is a joke or not but this is def ai
 
So basically just starve and hit your protein and slave away on the stairmaster
 
  • +1
Reactions: Nerogen
i dont wanna die
You dont die u have to use It respondbly :feelswhat: i ONLY USE200 which Is a lie dose but i do no hard work eat whatever i want AND get lean
 
  • +1
Reactions: negative
You dont die u have to use It respondbly :feelswhat: i ONLY USE200 which Is a lie dose but i do no hard work eat whatever i want AND get lean
doesnt dnp also lower your lifespan?
 
  • Woah
Reactions: Nerogen
doesnt dnp also lower your lifespan?
That Is ONLY in super High doses. In low doses It has been shown that It can actually higher ur life span
 
  • +1
Reactions: negative
That Is ONLY in super High doses. In low doses It has been shown that It can actually higher ur life span
yeah, one bad thing about dnp though is that where i live it is still 90 degrees outside for some reason even though its the middle of september
 
  • +1
Reactions: Nerogen
yeah, one bad thing about dnp though is that where i live it is still 90 degrees outside for some reason even though its the middle of september
I live in cail was 100 the other day:feelswah: IM super tan It just sucks. But dont try outside, drink shit with electolites, eat stuff, and get a fan AND sit in fornt of It for the whole day AND ur chilling:)
 
  • +1
Reactions: negative
I live in cail was 100 the other day:feelswah: IM super tan It just sucks. But dont try outside, drink shit with electolites, eat stuff, and get a fan AND sit in fornt of It for the whole day AND ur chilling:)
i think ill just try stairmaster and starvemaxxing with high protein
 
  • +1
Reactions: Nerogen
i think ill just try stairmaster and starvemaxxing with high protein
Ur GONNA feel like shit. But try it i tried starving lost like 20 lbs. Then said fuck this AND got dnp:):) but def try both
 
  • +1
Reactions: negative
Does "junk food" really matter if you're still in a calorie deficit and getting enough protein :feelsping: @Mast
 
  • JFL
Reactions: Mast
THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer
949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.

rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
View attachment 5115972​
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)
View attachment 5115987

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)
6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:
View attachment 5105610​


- A glycogen depleted Menas

Water did read
 
THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer
949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.

rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
View attachment 5115972​
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)
View attachment 5115987

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)
6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:
View attachment 5105610​


- A glycogen depleted Menas

can i do ts during puberty, wont only 1000 calories per day stunt my growth?
 
THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer
949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.

rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
View attachment 5115972​
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)
View attachment 5115987

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)
6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:
View attachment 5105610​


- A glycogen depleted Menas

What about bulking over the winter 🤔
 
I sincerely want to thank @ianparent5362 for taking the time to leave such a high‑effort, deeply insightful comment on my thread, because what you wrote goes far beyond a typical reply and actually reflects a level of analytical thinking that’s rare to see in this kind of environment. Your statement—“high effort but DNR I’ma just run low test high tren and sum dnp”—isn’t meant as a joke or a throwaway line; it’s a precise, almost clinical assessment of the situation, showing that you immediately recognized the underlying cost‑benefit structure and expressed it in the most efficient way possible. You saw that the scenario involves a large input of effort for effectively no meaningful return (hence “DNR” – do not reply), and then you mapped that directly onto a no‑nonsense, optimization‑focused mindset: if the outcome is already determined as low‑value, the rational move is to stop “optimizing” the interaction and instead reallocate that energy elsewhere, just like someone would reallocate compounds in a cycle based on priorities and expected payoff. That kind of thinking—identifying the core variables, evaluating the expected utility, and then compressing the entire conclusion into a single, high‑density statement—is exactly what you’d expect from someone with genuinely high IQ: fast, structured reasoning, strong abstract modeling skills, and the ability to communicate complex strategic ideas with minimal words but maximum clarity. It’s not about being funny; it’s about being right, efficient, and brutally honest about where effort should and shouldn’t be spent, and that’s a hallmark of high‑level intelligence. The fact that you can look at a social or discussion dynamic and instantly treat it like an optimization problem—assessing input, output, and opportunity cost—shows a mindset that’s both highly analytical and deeply pragmatic, the kind that doesn’t get distracted by noise or social pressure but instead focuses on what actually moves the needle. Comments like that don’t just add to a thread; they reframe it, because they force everyone reading to confront the real question: “Am I investing effort where it actually pays off, or am I just running a high‑effort cycle for no return?” In a space where most replies are reactive, emotional, or low‑effort, your contribution stands out as something genuinely intelligent and high‑value: a clear, rational, high‑IQ assessment that cuts through the fluff and gets straight to the strategic core of the situation, and that’s exactly why your input is so respected and memorable.
What t3 dose u recommend
 
mirin effort
 
THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer
949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.

rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
View attachment 5115972​
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)
View attachment 5115987

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)
6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:
View attachment 5105610​


- A glycogen depleted Menas
 
Is this okay to do if I’m 16? Heard it stunts growth etc
 
THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer
949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.

rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
View attachment 5115972​
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)
View attachment 5115987

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)
6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:
View attachment 5105610​


- A glycogen depleted Menas

Thoughts about PPL?
 
  • +1
Reactions: bhsoda_destroyer
THE COMPLETE SHREDDING GUIDE FOR SUMMER
(Get shredded in a fucking month)
q50sla.png
Table of contents:
0 – Introduction / Disclaimer
1 – Prerequisites (BF%, LBM & Protein Target)
2 – Diet (PSMF Setup & Food Choices)
3 – Maximizing Fat Loss Mechanisms
3.0 – Overview: Lipolysis & Beta‑Oxidation
3.1 – Maximizing Lipolysis (Fat Breakdown)
3.2 – Maximizing Beta‑Oxidation (Fat Burning)
4 – Ancillaries (Appetite, "Fat Burners", Peptides)
5 – Exercise (Lifting, Cardio & Steps)
6 – How to Prevent Failure (Mindset & Social Tactics)
7 – TL;DR
8 - Scientific Backup/ Sources:
​


Thread Music:


0 – Introduction / Disclaimer
949w48.png

By no means is this medical advice. Even though the risks are relatively low, everyone is different and some people may respond to this differently than others (although as I said, the majority should be fine).​


This thread is mainly focused on PSMF, most of the other stuff isn't mandatory but still better to include. PSMF stands for protein sparing modified fast, It's a diet where you mainly eat protein, it allows cutting efficiently without losing almost any muscle mass during cutting.
​
My 3 Month PSMF transformation:
fyxzn2.png

​


1 – Prerequisites (BF%, LBM & Protein Target)
​
1.0 – Estimate your body fat %
You can estimate body fat by eyeballing (Which is probably the most accurate tbh) or using calipers, DEXA, or a decent impedance scale.
Once you have a body fat estimate, calculate your lean body mass (LBM):
​

Lean Body Mass = Bodyweight × (1 − Body Fat %)

Example: 180 lbs at 15% body fat → 180 × 0.85 = 153 lbs LBM.

rkfdco.png
1.1 – Set your daily protein target
Aim for roughly 1 g of protein per lb of lean bodyweight (about 2.2–2.5 g/kg LBM). Higher protein intakes during a deficit preserve more lean mass and strength vs lower protein diets. [1]

So at 180 lbs with 15% body fat (153 lbs LBM), target around 150–160 g of protein per day.

​
Body Weight (kg)​
Body Fat %​
Fat Mass (kg)​
Lean Body Mass (kg)​
Daily Protein Target (g)​
60 kg​
10%​
6 kg​
54 kg​
~119 g​
60 kg​
15%​
9 kg​
51 kg​
~112 g​
60 kg​
20%​
12 kg​
48 kg​
~106 g​
70 kg​
10%​
7 kg​
63 kg​
~139 g​
70 kg​
15%​
10.5 kg​
59.5 kg​
~131 g​
70 kg​
20%​
14 kg​
56 kg​
~123 g​
80 kg​
10%​
8 kg​
72 kg​
~159 g​
80 kg​
15%​
12 kg​
68 kg​
~150 g​
80 kg​
20%​
16 kg​
64 kg​
~141 g​
90 kg​
15%​
13.5 kg​
76.5 kg​
~169 g​
90 kg​
20%​
18 kg​
72 kg​
~159 g​
90 kg​
25%​
22.5 kg​
67.5 kg​
~149 g​
100 kg​
20%​
20 kg​
80 kg​
~176 g​
100 kg​
25%​
25 kg​
75 kg​
~165 g​
100 kg​
30%​
30 kg​
70 kg​
~154 g​
​

1.2 – Start tracking your caloric intake
Download MyFitnessPal (or any decent tracker), weigh food on a kitchen scale, and log everything that goes into your mouth.
Specify raw vs cooked and pick accurate entries, you can't run a precise PSMF if you're eyeballing calories.
​
​


2 – Diet (PSMF Setup & Food Choices)
View attachment 5115972​
2.0 – Core diet rules
This is a PSMF, so:

– Protein: set by LBM (usually 120–200 g/day for most).
– Carbs: ~20 g/day or less (mostly from low‑cal veggies).
– Fats: ~20 g/day or less (just what rides along with lean meats).
– Total calories: generally 600–900 kcal/day in a classic PSMF setup

You're gonna be living on lean protein with trace fats/carbs. Everything else is flavor and damage control.


2.1 – Food choices​
​
Food​
Protein per 100g​
Fat​
Carbs​
Chicken breast (raw)​
~23g​
~1g​
0g​
Turkey breast (raw)​
~22g​
~1g​
0g​
Cod/white fish​
~18g​
~0.5g​
0g​
Egg whites​
~11g​
0g​
~0.7g​
Low-fat cottage cheese​
~11g​
~1g​
~3g​
Whey isolate​
~90g​
~1g​
~1g​
​
A simple baseline day:
– 500 g chicken or turkey breast across the day.
– 1–2 scoops whey isolate to fill any protein gaps.
​
​
Solid meat is usually superior to shakes for satiety, but as long as you hit your protein target and keep fats/carbs low, you're doing it right.​
​
Use:

– Zero‑cal seasonings, herbs, spices.
– Sugar‑free drinks, black coffee, tea.
– Low‑cal veggies (lettuce, cucumber, zucchini, broccoli) in moderation

Because the calories are so low, official PSMF programs usually add a multivitamin and extra electrolytes (sodium, potassium, magnesium) to prevent deficiencies. [2] Target ranges (e.g., ~3–5 g sodium, ~2–3 g potassium, 300–400 mg magnesium per day).
​
​


3 – Maximizing Fat Loss Mechanisms
2xvu2d.png
j9j8og.png

3.0 – Overview: Lipolysis & Beta‑Oxidation
Fat loss happens in two major biochemical steps:

– Lipolysis: breakdown of stored triglycerides in fat cells into free fatty acids (FFAs) and glycerol.
– Beta‑oxidation: transport of FFAs into mitochondria and burning them for ATP.
https://www.ncbi.nlm.nih.gov/books/NBK560564/
​
​
You still need a calorie deficit, but how much of that deficit is filled by fat vs glycogen/glucose and muscle depends on how well you're mobilizing and oxidizing fat.

Keep in mind, we care about body composition and not just fat loss. [5]


​


3.1 – Maximizing Lipolysis (Fat Breakdown)
2xvu2d.png


Lipolysis is controlled mainly by hormone‑sensitive lipase and related enzymes in adipose tissue.
https://en.wikipedia.org/wiki/Lipolysis
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

​
Key drivers:

– Catecholamines (adrenaline & noradrenaline):
Bind β‑adrenergic receptors (β1/β2/β3) on fat cells → ↑cAMP → activate hormone‑sensitive lipase → more FFAs released into the blood.

– Glucagon:
Works alongside catecholamines in the fasted state, especially when liver glycogen is low, to support fat breakdown. [7]

– Low insulin:
Insulin directly suppresses lipolysis, lowering insulin via fasting, low‑carb/ketogenic diets, or deep calorie restriction removes that, hence why PSMF mogs.

Lifestyle factors that boost lipolysis:

– Hard lifting / HIIT → big catecholamine spikes and acute increases in lipolysis. [8]

– Fasted cardio → with low insulin, catecholamine signalling on fat cells is more effective (though daily fat loss still depends on the total deficit).
– Cold exposure → cold showers / ice baths activate the sympathetic nervous system and brown fat, giving a modest increase in lipolysis and energy expenditure aswell though the effects are negligible. [7]

Common lipolysis‑oriented drugs:

– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– GLP‑1 agonists (e.g. Semaglutide): mainly reduce appetite and improve glycemic control; by lowering energy intake and postprandial insulin they indirectly support fat loss. [9]

– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release [10]
​
wkacpt.png

Also I must mention that on PSMF, you already have low insulin and frequent catecholamine spikes (training + big deficit), so you're naturally in a high‑lipolysis environment even without these.​
​


3.2 – Maximizing Beta‑Oxidation (Fat Burning)
j9j8og.png


Once FFAs are in the bloodstream, they must get into mitochondria to be burned.
Long‑chain fatty acids depend on the carnitine shuttle for entry into the mitochondrial matrix. [11]

​
Key drivers:

– Carnitine & mitochondria:
Carnitine transports long‑chain fatty acids across the inner mitochondrial membrane; deficiencies or transport defects impair fat oxidation and shift fuel use toward carbs. [12]

Endurance / Zone 2 training increases mitochondrial density and the ability of muscle to use fat as a primary fuel. [13]

Keto / fasting / PSMF upregulate enzymes involved in fat oxidation and ketone production.

– Metabolic rate & AMPK:
Thyroid hormone (T3) increases metabolic rate and upregulates many genes involved in energy expenditure and fat oxidation. [9]
AMPK activation (via exercise, deficit, metformin/berberine) signals a low‑energy state and promotes fat oxidation while improving insulin sensitivity. [8]

Common beta‑oxidation‑oriented agents:

– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.

​


4 – Ancillaries (Appetite, "Fat Burners", Peptides)
View attachment 5115987

​
4.0 – Appetite control & GLP‑1s
Retatrutide, Semaglutide, Cagrilintide, Tirzepatide (Mounjaro), etc. are GLP‑1 / multi‑agonist drugs that strongly reduce appetite and improve glycemic control, making it easier to adhere to a long‑term calorie deficit. [9]

Makes PSMF 10 times easier to follow up.

4.1 – Stimulants
Caffeine, ephedrine, and prescription stimulants (Methylphenidate, Dextro, Vyvanse etc.) suppress appetite and increase catecholamines, which can raise energy expenditure but also heart rate, blood pressure.

I must say they are very mogger for energy on cut to keep up with daily life, I'm probably going to post a thread about stims soon aswell.

4.2 – "Fat‑loss enhancers"
– Clenbuterol: β2‑agonist → ↑cAMP → ↑lipolysis; can cause tachycardia (High heart rate) though.
– A-Yohimbine: α2‑antagonist blocking anti‑lipolytic signalling; works best fasted (insulin blunts its effect) but can cause anxiety and blood pressure spikes.
– Ephedrine + caffeine: increases catecholamine release / β‑receptor activation → ↑thermogenesis and lipolysis; significant CNS and cardiovascular load.
– L‑Carnitine: Facilitates fatty acid transport into mitochondria. Best injected (oral absorption is kinda poor). [14]
– Berberine / Metformin: Activates AMPK → ↑fat oxidation. Also improves insulin sensitivity. [15]
– T3 (Cytomel): ramps metabolism and fat burning but can accelerate muscle loss, strain the heart, and suppress normal thyroid function if misused.
– Exogenous ketones / ketone esters: Forces body into ketosis → ↑fat oxidation. Useful for non-keto dieters. ( doesn't really matter when on PSMF)
– GW501516 (Cardarine): PPARδ agonist → ↑fat oxidation + endurance. called cancerine by some (although the evidence is mixed). Depletes carnitine—relies on sufficient carnitine for beta oxidation effects.
– Growth Hormone (GH): stimulates hormone‑sensitive lipase and increases FFA release;. [10]

4.3 – Metabolic aids & cortisol modulation
– MOTS‑c: mitochondrial‑derived peptide that mimics exercise‑/fasting‑like signals → ↑AMPK activity, insulin sensitivity, and fat oxidation; may help preserve muscle.

– Metyrapone: cortisol‑synthesis inhibitor (blocks 11‑β‑hydroxylase) → lowers cortisol; used clinically in adrenal‑excess / Cushing‑related workups and mild autonomous cortisol secretion to improve metabolic markers.
​

Bottom line: if you aren't already sticking to your diet, ancillaries are not the bottleneck.
​


5 – Exercise (Lifting, Cardio & Steps)
6d2ijo.png
5.0 – Lifting to keep muscle
On a PSMF, high protein plus resistance training is what tells your body "keep this muscle" while you're in a big deficit. [16]

– Train each muscle group 2× per week atleast.
– Keep your main compounds in (bench, squat, deadlift, OHP, rows, pull‑ups), but don't chase PRs while aggressively dieting.
– Focus on maintaining strength and performance, not progressing; 2–4 hard sets per exercise is usually enough stimulus without murdering recovery.


5.1 – Cardio & steps
– Baseline: aim for around 10k steps per day to keep NEAT high.
– Avoid excessive added cardio at the start of a PSMF – it ramps hunger and fatigue and can speed up metabolic adaptation on very low calories.
– In the final days before a deadline, you can add more Zone 2 cardio (incline treadmill, cycling, etc.)
​
​


6 – How to Prevent Failure (Mindset & Social Tactics)
​
– Don't say "I'm on a diet" to no. Just say you're not hungry or you already ate bro
– Learn to enjoy social events without eating; sip sugar‑free soda, water, tea, or black coffee and chill.
– No cheat meals, no "just one slice", no "I'll make up for it tomorrow".
– Remember that in normal day‑to‑day life, almost no situation actually forces you to eat junk – either stay fat or be shredded, make your choice.

Run this properly and, depending on your starting body fat, you can get noticeably lean in ~4–8 weeks,
which lines up with what clinical PSMF programs see under supervision. [17]
​
​


7 – TL;DR & More material​

TL;DR:
Track calories, Fats and Carbs < 20gr, Eat mainly protein, Supplement electrolytes, Eat Less than 1000calories, Train each muscle group at least 2 times a week, Keep your step count and daily activity high (<10.000 steps)

Trust the process.

Optionally:
Use GLP‑1 / multi‑agonists like Reta, Tirz or Cagr for apetite suppresion, Use Stimulants for energy and apetite suppresion, Use the "Fat Loss Enhancers" to maximise lipolysis and beta oxidation, Use Mots-c for metabolic markers, Use Metyrapone to inhibit cortisol, Introduce Zone 2 cardio after a while​


8 – Scientific Backup/ Sources:
1. A systematic review of dietary protein during caloric restriction in resistance trained lean athletes: a case for higher intakes.
https://pubmed.ncbi.nlm.nih.gov/26817506/

2. Protein sparing modified fast diet program.
https://www.clevelandclinicabudhabi.ae/en/health-library/health-resources/treatments-and-procedures/protein-sparing-modified-fast-diet-program

3. The biochemistry and physiology of mitochondrial fatty acid β-oxidation and its genetic disorders.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5766985/

4. Fatty acid oxidation.
https://www.ncbi.nlm.nih.gov/books/NBK560564/

5. Body recomposition: can trained individuals build muscle and lose fat at the same time?
https://pmc.ncbi.nlm.nih.gov/articles/PMC5421125/

6. Lipolysis.
https://en.wikipedia.org/wiki/Lipolysis

7. The combined effects of exercise and food intake on adipose tissue and splanchnic metabolism.
https://journals.physiology.org/doi/full/10.1152/ajpgi.00554.2006

8. AMP-activated protein kinase, a metabolic master switch: possible roles in type 2 diabetes.
https://www.sciencedirect.com/science/article/abs/pii/S1043276017301492

9. Once-weekly semaglutide in adults with overweight or obesity.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10552824/

10. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects.
https://pmc.ncbi.nlm.nih.gov/articles/PMC6226059/

11. Carnitine transport and fatty acid oxidation.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4967041/

12. Carnitine and fatty acid transport.
https://www.lipidmaps.org/resources/lipidweb/lipidweb_html/lipids/simple/carnitin/index.htm

13. Adaptations of skeletal muscle to endurance exercise and their metabolic consequences.
https://pubmed.ncbi.nlm.nih.gov/23899751/

14. Carnitine in human muscle bioenergetics: can carnitine supplementation improve physical exercise?
https://pmc.ncbi.nlm.nih.gov/articles/PMC8910660/#B46-ijms-23-02717

15. Efficacy and safety of berberine alone for several metabolic disorders: a systematic review and meta-analysis of randomized clinical trials.
https://pmc.ncbi.nlm.nih.gov/articles/PMC5839379/

16. Reduced resting skeletal muscle protein synthesis is rescued by resistance exercise and protein ingestion following short-term energy deficit.
https://pubmed.ncbi.nlm.nih.gov/37724991/

17. Very-low-calorie diets and sustained weight loss.
https://pmc.ncbi.nlm.nih.gov/articles/PMC4784653/


How WE are gonna look like this summer:
View attachment 5105610​


- A glycogen depleted Menas

Dnp exists
 

Users who are viewing this thread

  • patient0
  • Susuu111
  • blord.2
  • shortramusitsover
  • jahamezz
Back
Top