



AlexoJeLTN
<HTN = Rope
- Joined
- Jul 31, 2025
- Posts
- 590
- Reputation
- 447
Before we begin, do not take anything i say as medical advice, this is all just theory
Table of contents:
Somatostatin(SST) is a hormone produced by hypothalamus (same as GH). The hypothalamus produces both GHRH and SST. Main function of SST is to act like a brake pedal towards growth (almost like FGFR3 but completely different mechanism). SST binds to SSTR1-5 which inhibits the pituitary gland to release GH, it also lowers insulin(SSTR5 mainly) and glucagon(SSTR2 mainly) secretion and bunch of other stuff
Since we know that GH and SST are antagonistic towards eachother, if we could block SST we would have more GH? Right? Welcome to SSTR inhibitors. SSTRs goes from 1 to 5, with SSTR2 and SSTR5 being the most involved in inhibiting GH(73% pubmed). There are 2 compouds that i could find, hence this is "niche" and not really known.
1. Cyclosomatostatin: Is a broad and non-selective SSTR antagonist
2. SSTR5 antagonist (aka compound 25a): Selectively targets SSTR5
3. SCO-240: Selectively targets SSTR5
1. Cyclosomatostatin: Is a broad and non-selective SSTR antagonist
2. SSTR5 antagonist (aka compound 25a): Selectively targets SSTR5
3. SCO-240: Selectively targets SSTR5
To mitigate sides I insantly thought about FGFR inhibition, when something like Tyra-300 is way better then Erda because it selectively inhibits FGFR3 instead of all of them, has way less sides, but in this scenario, its completely different mechanism, because they all just do 1 thing and thats antagonise SST, so less inhibition = less GH
Now onto side effects: Basically everything HGH would have(since we are boosting our GH) + everything SST regulates.
First of all SST blocks insulin, so we would just have a bunch of insulin going around (insulin resistance is unrelated btw) and our blood sugar would be just too low(hypoglycemia). Then we have GI stuff like cramps, bloating, diarrhea. Increased BP, worsen sleep, memory, etc. basically messes with the CNS.
Now onto side effects: Basically everything HGH would have(since we are boosting our GH) + everything SST regulates.
First of all SST blocks insulin, so we would just have a bunch of insulin going around (insulin resistance is unrelated btw) and our blood sugar would be just too low(hypoglycemia). Then we have GI stuff like cramps, bloating, diarrhea. Increased BP, worsen sleep, memory, etc. basically messes with the CNS.
This is by far the most important to read, dont DNR.
(every study will be linked btw)
SSTR inhibitors dont have much studies, but this was the most interesting one: here
Lets start with the most interesting thing and thats IGF1. The study shows noticably increased IGF1 and shows that both 3mg and 80mg oral SSTR5 antagonist c25a had noticable increase in IGF1, take a look at this graph

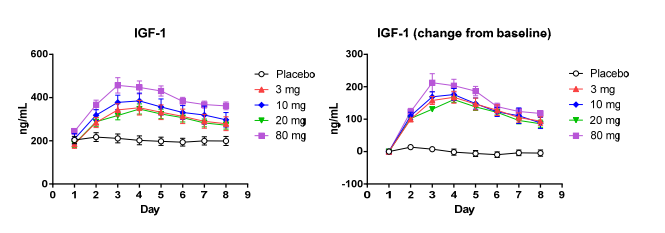
As you can see higher dosage is obviously more effective but only slightly, and you would need a really high difference something like 3mg vs 80mg to actually see a difference. Btw it took me some time but i found supplementary data if anyone is interested. Basicall you can see the ng/mL

Now what about the dangerous stuff, like insulin or other hormones?? Take a look

Its only 7 day study, but this indicates that goes up more then the placebo but its not really high or anything, and when we compare studies on HGH about insulin resistance, like this one, we see in just 5 days it went 2.7x above baseline, and here nothing.
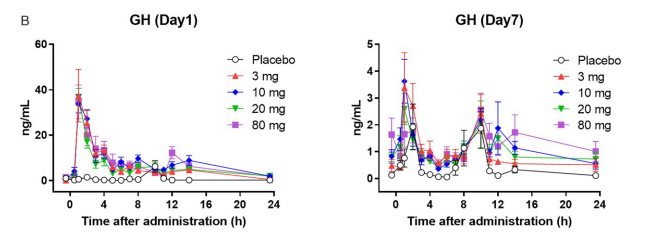
Anyway here is some other stuff u can check out, it doesnt really indicate a significant change in hormones:

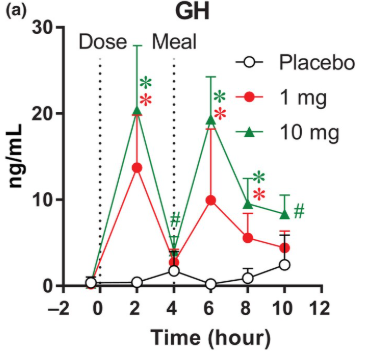
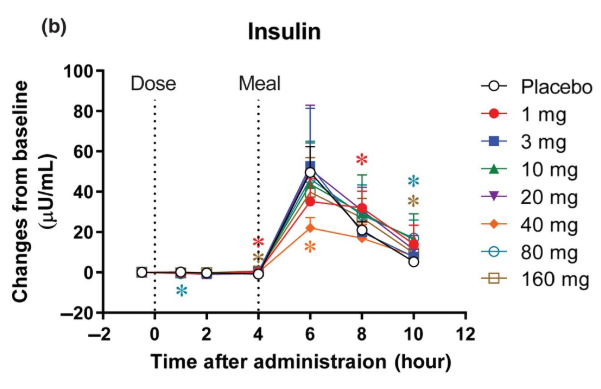
This study is also interesting, about SSTR5, as we can see, there is increased GH and that 10mgs mogs 1mg. Insulin is again like the same in every dosage, it almost seems like low dosage antagonizes SSTR5 just as much as high dosage. Also important to mention, this article on SCO-240 reported on higher triglycerides in 1 participant from groups 1mg, 20mg, 40mg and 80mg, seems like its related to SCO-240


Other studies:
In this study, we can actually see not just that glucose drops, but it also acts like a GLP1 agonist
This study reports on increased insulin sensitivity
This study reports on how MK-678 activates SSTR2, which in pituitary cells reduces L-type Ca²⁺ signaling which potentionally could end up in less active osteoblasts (we dont want that)
This study shows how in diabetics selectively targeting SSTR5 inhibition we can lower our insulin, hba1c and increase insulin sensitivity
Now the first study alone shows that inhibiting ONLY SSTR5 gives a nice IGF1 increase, so what if we were to inhibit more? Would there be more IGF1? more sides?
I dont know, genuinely have no idea, but i mean probably
(every study will be linked btw)
SSTR inhibitors dont have much studies, but this was the most interesting one: here
Lets start with the most interesting thing and thats IGF1. The study shows noticably increased IGF1 and shows that both 3mg and 80mg oral SSTR5 antagonist c25a had noticable increase in IGF1, take a look at this graph
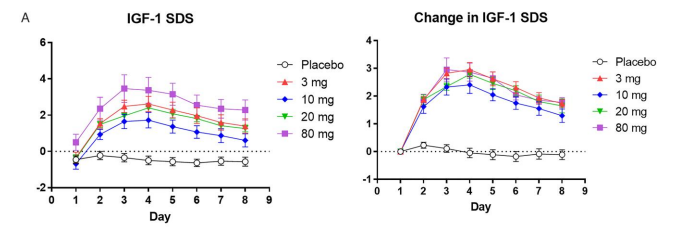
As you can see higher dosage is obviously more effective but only slightly, and you would need a really high difference something like 3mg vs 80mg to actually see a difference. Btw it took me some time but i found supplementary data if anyone is interested. Basicall you can see the ng/mL
Now what about the dangerous stuff, like insulin or other hormones?? Take a look
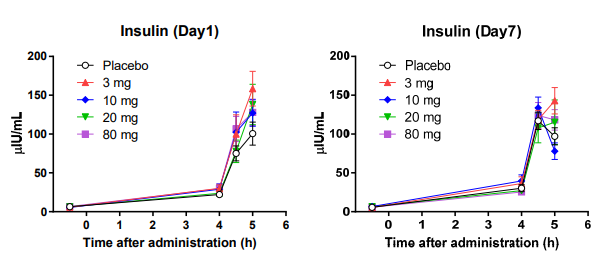
Its only 7 day study, but this indicates that goes up more then the placebo but its not really high or anything, and when we compare studies on HGH about insulin resistance, like this one, we see in just 5 days it went 2.7x above baseline, and here nothing.
Anyway here is some other stuff u can check out, it doesnt really indicate a significant change in hormones:
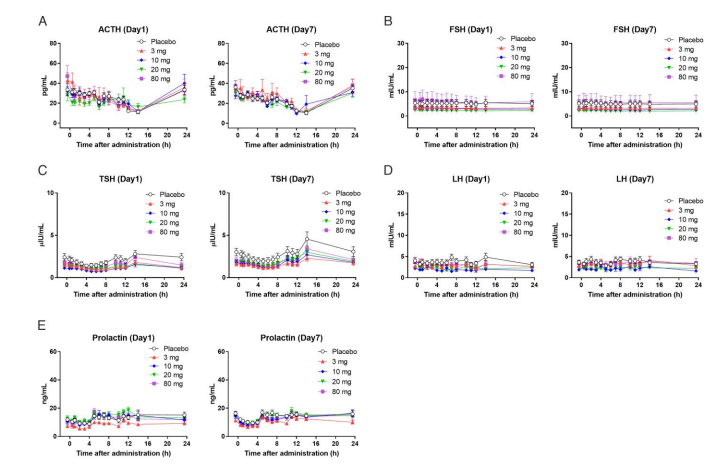
This study is also interesting, about SSTR5, as we can see, there is increased GH and that 10mgs mogs 1mg. Insulin is again like the same in every dosage, it almost seems like low dosage antagonizes SSTR5 just as much as high dosage. Also important to mention, this article on SCO-240 reported on higher triglycerides in 1 participant from groups 1mg, 20mg, 40mg and 80mg, seems like its related to SCO-240
Other studies:
In this study, we can actually see not just that glucose drops, but it also acts like a GLP1 agonist
This study reports on increased insulin sensitivity
This study reports on how MK-678 activates SSTR2, which in pituitary cells reduces L-type Ca²⁺ signaling which potentionally could end up in less active osteoblasts (we dont want that)
This study shows how in diabetics selectively targeting SSTR5 inhibition we can lower our insulin, hba1c and increase insulin sensitivity
Now the first study alone shows that inhibiting ONLY SSTR5 gives a nice IGF1 increase, so what if we were to inhibit more? Would there be more IGF1? more sides?
I dont know, genuinely have no idea, but i mean probably
What SSTR inhibitor seems to be the best? SCO-240 has the best studies
What dosage should we take? Probably how much u can afford, it can be 3, 5, 10, 20, 40mg doesnt matter
Is this affordable? Not at all, from what i found 5mg cost like 300-400euro
Isnt HGH better and more studied? Yes it is lmao
Is this even available? Hell no
Should we even take this? I dont think so, this seems like a weaker version of HGH, its less studied, we dont know what could happen over a longer period of time, its expensive, unavailable and just a risk
Pros: IGF1, low sides, oral(ig)
Cons: Literally anything else
What dosage should we take? Probably how much u can afford, it can be 3, 5, 10, 20, 40mg doesnt matter
Is this affordable? Not at all, from what i found 5mg cost like 300-400euro
Isnt HGH better and more studied? Yes it is lmao
Is this even available? Hell no
Should we even take this? I dont think so, this seems like a weaker version of HGH, its less studied, we dont know what could happen over a longer period of time, its expensive, unavailable and just a risk
Pros: IGF1, low sides, oral(ig)
Cons: Literally anything else
Thanks for reading this, this took me some time to make and its nothing really serious but for me it was fun diving into some niche compound.
If you read this, u have now have ELITE ball knowledge and could give me rep
Attachments
Last edited:


