

jnxy
Old @: paul.jnxy
- Joined
- Jan 10, 2026
- Posts
- 4,386
- Reputation
- 6,230
- OP
- #151
Nighas when they realise velocity does not equal FAHTamox lowers igf1 buddy pretty counter intuitive dont you think
Follow along with the video below to see how to install our site as a web app on your home screen.
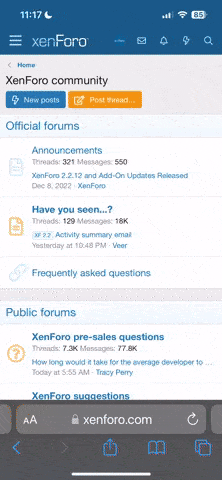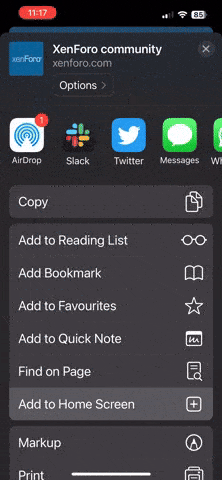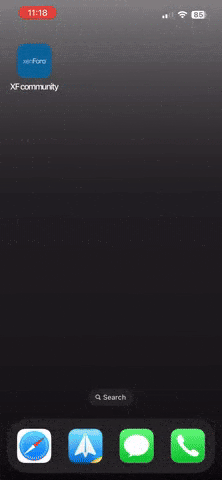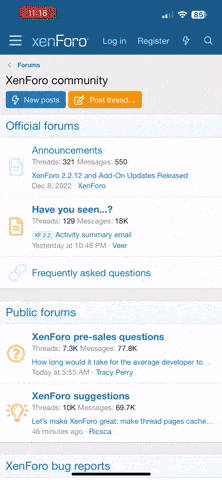
Note: this_feature_currently_requires_accessing_site_using_safari


Nighas when they realise velocity does not equal FAHTamox lowers igf1 buddy pretty counter intuitive dont you think

Nigga if you increase the duration of growth but slow down the growing itself you dont get anywhere do you, im not against using tamox i think its a good idea but you js failed to mention the countless studies that show it lowers igfNighas when they realise velocity does not equal FAH
So what if it does? You can pair it with shit to upregunate IGF-1R sensitivity and increase IGF1 artificially. Nobody is claiming it’s good alone. You can’t heightmax with one single axis. It’s over if you do.Nigga if you increase the duration of growth but slow down the growing itself you dont get anywhere do you, im not against using tamox i think its a good idea but you js failed to mention the countless studies that show it lowers igf
I just read this tf. My bad G. Tamox acts as a Estrogen receptor alpha antagonist inside the plates. You literally are DEGRADING the receptor.What a great way to tell the growth plates to raise e2 sensitivity even more instead of degrading the receptor!! Lets just antagonise it!! Didn't read tho good work

would this stack go well with 6-8IU HGH?Yes. A combo imo is best. Im currently on 12.5 mg aromasin (eod) + 0.625 letro (eod) and 10 mg Tamoxifen ed without being on any androgens. I will be upping them more when I hop on androgens and if I tolerate them will double all the doses.


 pubmed.ncbi.nlm.nih.gov
Atleast 20+ for maximum effectivenesswould this stack go well with 6-8IU HGH?
will read and reply tmrw. It’s getting lateStudies on women with breast cancer show elevated IGFBP levels = bad ratio = less growth. BMD is not the factor to use
Studies like the one I'll list are better but still not enough. Evidence is too conflicted to draw conclusions.
The use of tamoxifen to improve height potential in short pubertal boys - PubMed
A retrospective chart review of 7 pubertal boys who were treated with tamoxifen was conducted to determine the effects of this therapy on skeletal maturation and predicted adult height. Tamoxifen significantly decreased the rate of skeletal maturation and increased the predicted adult height...
You are right. We have barely enough evidence to draw an consensus on its effects on ERA AF1/2. (considering the study only used 7 kids). If I am not mistaken we do have mouse models were tamoxifen worked as an antagonist on ERA AF2 specifically. AF1 mostly is still partially or fully active. There are tons of studies showing tamoxifen did not increase FAH or change anything puberty wise (kids with gyno) and the kids were PAH increased by 10 cm/s were all on growth hormone. Indicating that it can be run in synergy with strong stimulation of the IGF1 axis. Ofc this is all theory. Sorry I’m at the gym rn.Studies on women with breast cancer show elevated IGFBP levels = bad ratio = less growth. BMD is not the factor to use
Studies like the one I'll list are better but still not enough. Evidence is too conflicted to draw conclusions.
The use of tamoxifen to improve height potential in short pubertal boys - PubMed
A retrospective chart review of 7 pubertal boys who were treated with tamoxifen was conducted to determine the effects of this therapy on skeletal maturation and predicted adult height. Tamoxifen significantly decreased the rate of skeletal maturation and increased the predicted adult height...

I've put a good 3 hours into this while eating my slop cereal with my primal raw milk. If you have learned anything from this thread please rep nigger. I need to fix my Post to rep ration.This content is for educational and informational purposes only and is not medical advice. I am not a doctor, and nothing here should be used to diagnose, treat, prevent, or cure any medical condition. Always consult a qualified healthcare professional before making decisions related to medications, supplements, hormones, training, or your health. I do not recommend trying any of these things on your own.
View attachment 5173557
This Threads song
What is Tamoxifen/Nolvadex
Quickly, Tamoxifen is a selective estrogen receptor modulator, or SERM.
View attachment 5176268
It binds competitively to estrogen receptors (ERs) in target cells. It acts as an antagonist in breast tissue by forming a receptor complex that recruits co-repressors instead of co-activators. This blocks estrogen-driven gene expression, reducing DNA synthesis and slowing the proliferation of estrogen-receptor-positive breast cancer cells.
In different tissues it shows mixed effects:
For you Sciencecels (like me):
- Antagonist in breast tissue.
- Agonist in bone (helps maintain density) and endometrium (increases certain risks).
The molecule features a central double bond allowing Z-isomer configuration which is critical for its activity. It is metabolized in the liver mainly by the CYP2D6 enzyme and makes it active in forms like 4-hydroxytamoxifen and endoxifen, which have higher affinity for the rEstrogen Receptors. This tissue-selective modulation makes tamoxifen effective for treating and preventing hormone-dependent breast cancers (For what it was orginally developed) while providing some estrogen-like benefits elsewhere.
View attachment 5176300
For what we as Heightmaxxers can use Nolvadex
Tamoxifen offers two main benefits for teenagers, particularly adolescent boys, when used off-label.
1. Height potential
E2 drives epiphyseal (growth plate) closure in both sexes during late puberty. Read my last thread about e2 HERE
THIS IS WELL DOCUMENTED for all of you retards disagreeing Google is free
I really recommend you read my last thread. This will make what im about to explain a lot easier.
Tamoxifen works in bone maturation by modulating estrogen receptor alpha (ERα) activity in growth plate chondrocytes.
During late puberty, e2 produced locally via aromatase from androgens or systemically binds to ERα in the epiphyseal growth plates. This activates ERα, which translocates to the nucleus and promotes gene expression that accelerates chondrocyte senescene, reduces proliferation in the proliferative zone, and stimulates hypertrophic differentiation and ossification. The net result is progressive advancement of bone age and eventual epiphyseal fusion, which halts linear growth.
Tamoxifen, as a SERM, binds competitively to ERα in bone tissue. It induces a receptor conformation that favors recruitment of co-repressors over co-activators in this context, thereby antagonizing estrogen’s maturational effects. This slows the rate of skeletal maturation without fully eliminating estrogen signaling. The result is a prolonged period of chondrocyte activity and delayed growth plate closure, extending the growth window.
Tamoxifen is only a partial antagonist in bone. Its SERM nature means it can exhibit some residual agonist-like effects or incomplete blockade depending on cellular context and co-regulator availability. It does not degrade the receptor. While it may not have the same effect as a full on SERD like Fulvestrant which binds ERα with high affinity, induces a different conformational change that leads to ubiquitination and proteasomal degradation of the receptor itself. Altough SERDs would theoretically offer far greater and more potent e2 suppression and more height gains they are typically not used due to them usually being injectable and having a far greater side effect profile. This is not what the thread is about tho.
To back these claims up I have some studies im gonna link.
The Primary Tamoxifen study for increasing FAH (Final adult height) is Kreher NC, Eugster EA, Shankar RR. The Use of Tamoxifen to Improve Height Potential in Short Pubertal Boys. Pediatrics. 2005.
Retrospective chart review of 7 short pubertal boys treated with tamoxifen. It showed significantly slowed skeletal maturation and increased predicted adult height (nearly 4 inches or 10 cms on average) without apparent negative effects on sexual maturation.
Keep in mind this is only on the e2 axis. A lot more can be done when this is paired with different biological pathways like the IGF-1/PTHrP/IHH or any other pathway for that matter.
If you want to ead a couple more very high IQ articles il link them here:
While this thread is focused only on SERMs go ahead and checkout some other Threads on much more studied Aromatase Inhibitors. I recommend you stack SERMs + AIs for maximal Growth.
- Review on delaying growth plate closure (2024): Discusses tamoxifen/SERMs as off-label options alongside more commonly studied aromatase inhibitors.ISPAE Journal
- Broader review on manipulating skeletal maturation (2021): Covers estrogen modulation (including SERMs and aromatase inhibitors) for height in various growth disorders.Frontiers in Endocrinology
2. Gynecomastia (enlarged breast tissue)
Pubertal gynecomastia is common due to temporary estrogen-androgen imbalance. Tamoxifen, as a SERM, blocks estrogen action specifically in breast tissue
I will not be going into depth on this topic as I am pretty sure there are some decent threads on Tamoxifen in the context of Gyno already.
Why People believe Tamoxifen does induce apoptosis and permanent Growth retardation
+ Why this is not True and retarded
When People say Tamoxifen causes permanent Growth Retardation they usually refer to this study here and this one
Which is generally retarded and JFL
Here is a quick Summary:
In an ex vivo organ culture of fetal rat metatarsal bones, tamoxifen caused dose-dependent shortening with increased chondrocyte apoptosis (via caspases and FasL/Fas). No recovery occurred after removal, indicating permanent arrest. A related in vivo follow-up (Karimian et al., 2008) in young male rats showed persistent shorter tibia and reduced cortical bone even after recovery, with elevated apoptosis and proliferation imbalance plus lower IGF-1.
The Reasearchers behind this paper identified a novel mechanism where tamoxifen activates the Fas ligand (FasL)/Fas death receptor pathway in chondrocytes. This leads to sequential caspase activation (caspase-8 first, then -9 and -3), executing apoptosis. This pathway is triggered independently of (or differently from) typical estrogen blockade, possibly due to tamoxifen’s unique receptor conformation in chondrocytes or non-genomic effects.
Basically Tamoxifen in a dose-dependent context activates a death recptor pathway leading to chondrocytes dying instead of multiplying (proliferation).
It's important that you notice the word dose-dependant. The Young (4-week-old) male Sprague-Dawley rats received 40 mg/kg/day tamoxifen (JFL
The important part is to now translate this into human dose which is usually done by using allometric scaling uses body surface area (BSA) via Km factors (FDA/EMA guideline approach):
Standard allometric scaling uses body surface area (BSA) via Km factors (FDA/EMA guideline approach):
- Identify animal dose: 40 mg/kg/day (rat).
- Rat Km factor (for ~150–250 g rat): 6.
- Human Km factor (adult 60–70 kg): 37.
- Conversion factor = Human Km / Rat Km = 37 / 6 ≈ 6.2.
- HED (mg/kg) = Rat dose (mg/kg) ÷ 6.2.
Calculation: 40 mg/kg ÷ 6.2 ≈ 6.45 mg/kg/day in humans.
Now translating this type of dose into a revelant daily human dose for a normal 60 kgs teen it would be ~387 mg/day (JFL
If we comapre this to the study where Tamoxifen significantly increased FAH the average dose was 20mg ed in spit dosage format (10mg morning 10mg evening)
This is a absurdly high dose considering 20 mgs a day is enough to give you amazing results. No non-tarded nigger is EVER i repeat EVER on such a high dose of Nolvadex. The rat-derived HED is roughly 15–40 times higher than common clinical doses used in adolescents.
I will now explain to "zhe Iqlets" why High rat doses trigger FasL and low human doses do NOT. (In before muh FasL will always be active muh
The FasL/Fas pathway activation by tamoxifen is dose and concentration dependent because it likely involves non-genomic, off-target effects that only become prominent when intracellular tamoxifen (or it metabolites) reaches sufficiently high levels. At lower concentrations, the dominant action is SERM-mediated ERα antagonism, which modulates gene expression without strongly engaging pro-apoptotic death receptor signaling.
At low nanomolar to low micromolar levels (typical of 20 mg human dosing), tamoxifen and its active metabolites primarily bind ERα with high affinity. This induces a specific receptor conformation that recruits co-repressors in certain tissues, blocking estrogen-driven transcription without broadly disrupting cell survival pathways. The FasL promoter or related signaling remains minimally affected or not at all.
In the micromolar range (as used in Chagin et al. ex vivo cultures), tamoxifen accumulates in cells and interacts with additional targets beyond ER: Tamoxifen can alter membrane fluidity, inhibit protein kinase C (PKC), or affect calcium signaling and oxidative stress pathways. These changes can indirectly promote transcription or secretion of FasL (via stress-activated kinases like JNK or other transcription factors). Secreted FasL then binds Fas (CD95) on the same or adjacent chondrocytes, forming the Death-Inducing Signaling Complex (DISC) with FADD, activating caspase-8 (initiator), which cascades to caspase-9 and -3. This extrinsic apoptosis pathway is efficiently engaged only above a concentration threshold where these secondary effects dominate.
Pour moi DNR Niggers: The scary permanent damage happened at absurdly high experimental doses no one uses. Standard 20 mg stays in the safe SERM zone.
We can also look at real-world data and documented evidence in pubertal boys with Gynecomastia:
Akgül S, et al. (2016). "The effect of tamoxifen on pubertal bone development in adolescents with pubertal gynecomastia." - link
Studied 20 boys treated with tamoxifen (at least 4 months). Assessed BMD, bone age, and height before and 1 year later. They found no significant effect on skeletal maturation (p=1.112). Bone mineralization increased as expected during puberty (Z-scores stable) and concluded Tamoxifen is safe for pubertal bone development and neither growth potential nor BMD was negatively affected. No signs of apoptosis-related damage or reduced height potential.
There are tons of other studies that your little lazy ahh can serach up and read yourself.
My personal advice is if you want to get meaningful height gains from Tamo you should not have any Gyno as the paper above showed no *significant* height gains. Fix your gyno first.
REP ME NIGGERS + REPLY WITH YOUR OPINION ON MY 150 IQ THREAD
thx ngaBumppppp
Would 2.5 letro eod and 10 tamox ed workYes. A combo imo is best. Im currently on 12.5 mg aromasin (eod) + 0.625 letro (eod) and 10 mg Tamoxifen ed without being on any androgens. I will be upping them more when I hop on androgens and if I tolerate them will double all the doses.
20 tamox ideally. Otherwise looking good.Would 2.5 letro eod and 10 tamox ed work

ThanksVery good thread,
What do you mean by this specifically?but why would one really use tamoxifen instead of the normal approach people talk about.
Better options then Tamox for a PCT. I’d use HCG/HMG.I read this more as life fuel for those planning to do a pct.
by the normal approach i mean hgh+ai. HCG/HMG are NOT PCT drugs. They do not restart pituitary signaling. hCG only mimics LH, while HMG provides FSH. Whereas enclomiphene and tamoxifen are SERMs; they block estrogen feedback at the hypothalamus, which then stimulates endogenous production of LH and FSH.Thanks
What do you mean by this specifically?
Better options then Tamox for a PCT. I’d use HCG/HMG.
IDK really know about PCTs, Im completely infertile so it does not matter to me for the time being until im out of puberty.by the normal approach i mean hgh+ai. HCG/HMG are NOT PCT drugs. They do not restart pituitary signaling. hCG only mimics LH, while HMG provides FSH. Whereas enclomiphene and tamoxifen are SERMs; they block estrogen feedback at the hypothalamus, which then stimulates endogenous production of LH and FSH.

Won’t do anything byitself.i started using tamoxifen 20mg ed for 2 days how much tamoxifen will increase my final adult height im 15.3 170cm and my bone age is around 14 15


